
Symptoms, examination, function, and imaging must be interpreted together.
Joint and musculoskeletal conditions
Ankle Osteoarthritis
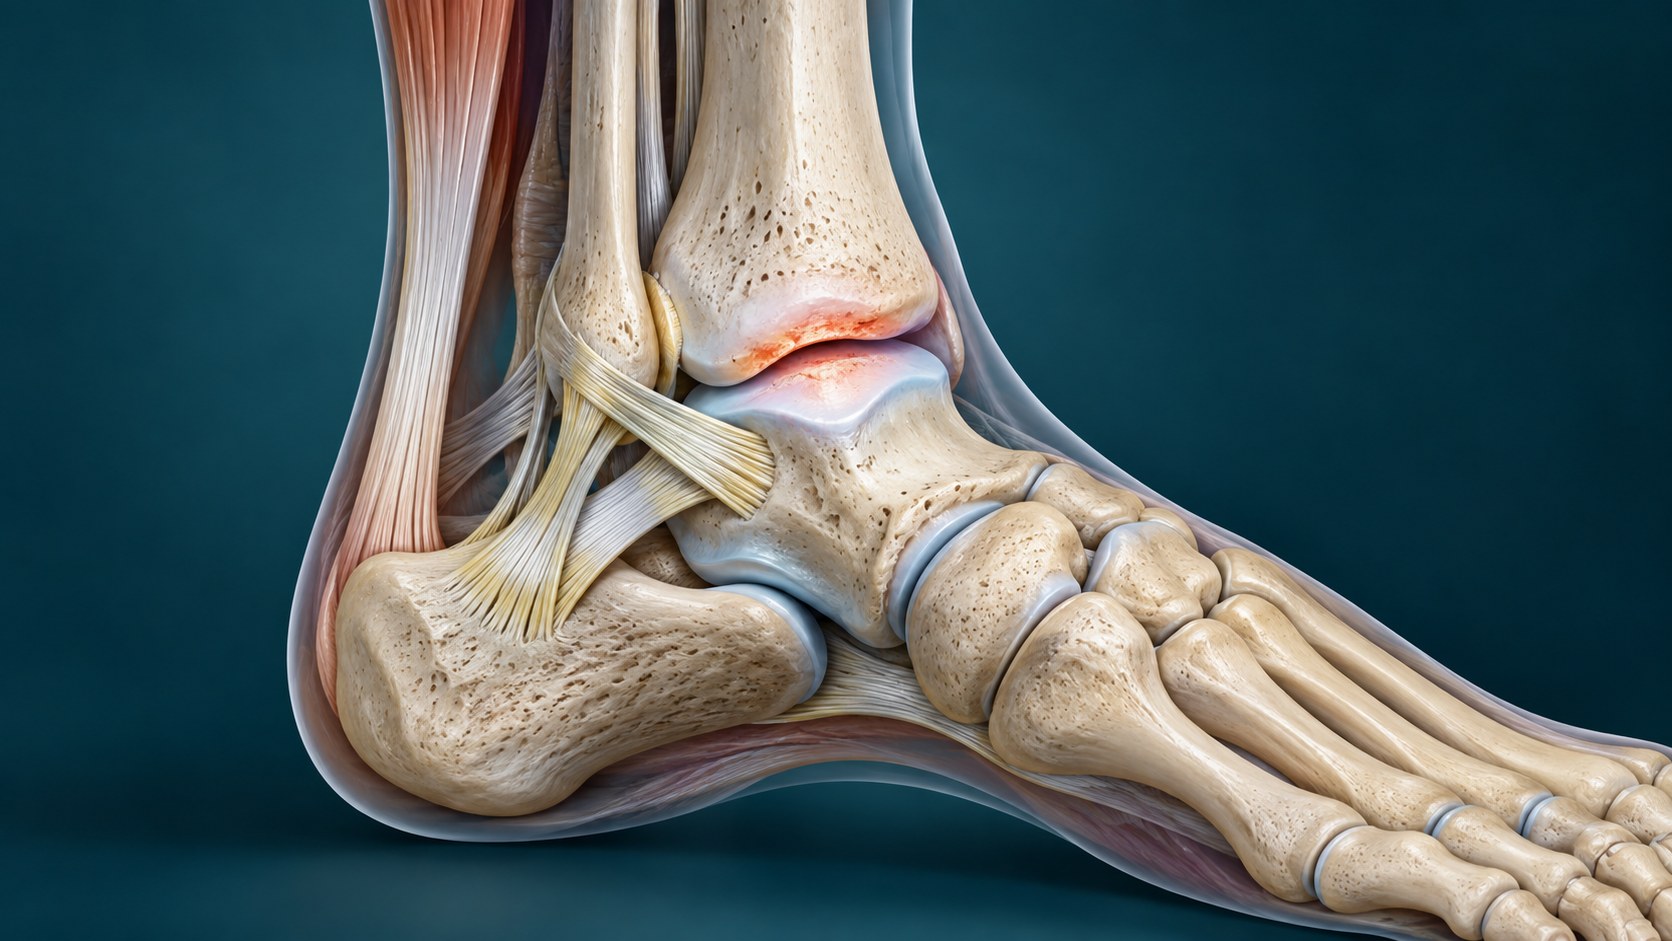
Ankle osteoarthritis can cause joint-line pain, stiffness, swelling, and reduced walking tolerance. Prior injury is common, but the diagnosis still requires correlation of symptoms, examination, function, and imaging.
Quick orientation
What to know first
Neighboring joints, tendons, nerves, and referred pain can overlap.
A procedure is one possible tool, not proof of the diagnosis or an automatic next step.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
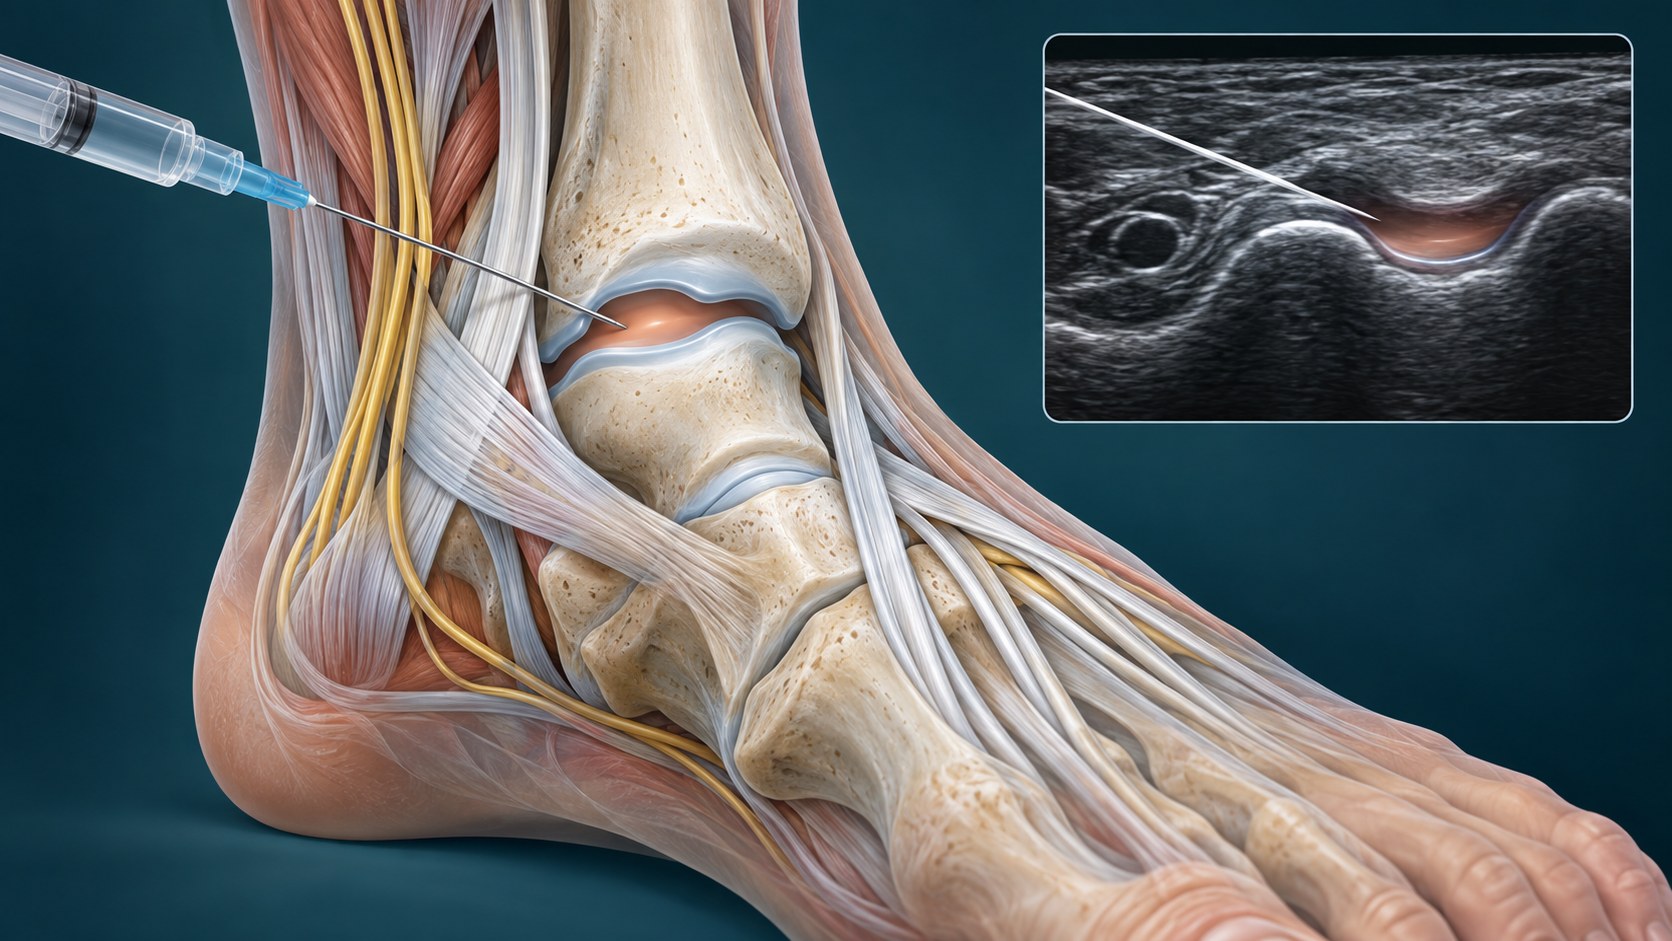
Ankle Joint Injection
May enter a reviewed treatment discussion for diagnosed ankle osteoarthritis after conservative-care and patient-selection review; generic Ankle Pain is not the primary diagnosis relationship.
Symptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Pain location and movement sensitivity can narrow the differential but rarely identify one structure alone.
Stiffness, range of motion, loading tolerance, weakness, swelling, and daily function add diagnostic context.
The pattern should be checked for referred pain, neurologic features, inflammatory disease, injury, and other alternatives.
Relevant anatomy
Anatomy and pain mechanisms
The tibiotalar joint joins the tibia and talus. Symptoms can overlap with the subtalar joint, tendons, ligaments, impingement, osteochondral injury, nerve disorders, and referred pain, so the painful region alone is not enough.
History and examination first
How the diagnosis is evaluated
Evaluation combines the history, movement and loading pattern, focused examination, functional goals, and selective imaging. Structural change can support a diagnosis, but imaging severity and symptom severity may not match.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Referred spinal or nerve-related pain
Tendon, bursa, muscle, or neighboring joint disorders
Inflammatory arthritis, infection, fracture, or another less common cause when the history suggests it
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, and movement matched to irritability
Progressive strength, mobility, and function when appropriate
Medication review that accounts for individual risks
Reassessment when the pattern changes or improvement stalls
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
The 2026 AAOS ankle guideline treats corticosteroid monotherapy as a consensus option for possible short-term symptom relief because direct evidence is insufficient.
A systematic review found no reliable efficacy signal for commonly studied ankle intra-articular products.
Education, individualized exercise, bracing, footwear, medication review, and surgical referral can each have a role according to the clinical problem.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
Fever, a hot swollen joint, or systemic illness
Major trauma or inability to bear weight or use the limb
Rapidly progressive weakness, numbness, or a new emergency symptom pattern
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the symptom pattern and meaningful functional limits
Examine the joint and neighboring regions before attributing symptoms to one structure
Review imaging only in clinical context
Choose among rehabilitation, medication review, a selected procedure discussion, or referral without assuming a fixed sequence
Common questions
Ankle Osteoarthritis FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Why is ankle arthritis different from knee or hip arthritis?
Ankle osteoarthritis is often post-traumatic and has a smaller evidence base, so findings from other joints cannot simply be transferred.
Does an X-ray explain all ankle pain?
No. Tendons, ligaments, neighboring joints, nerves, and other conditions can contribute.
Do injections rebuild ankle cartilage?
No. Available injections are not established as cartilage-restoring treatments.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
