
The anatomical target determines which type of treatment is being discussed.
Treatment guide
Neuromodulation
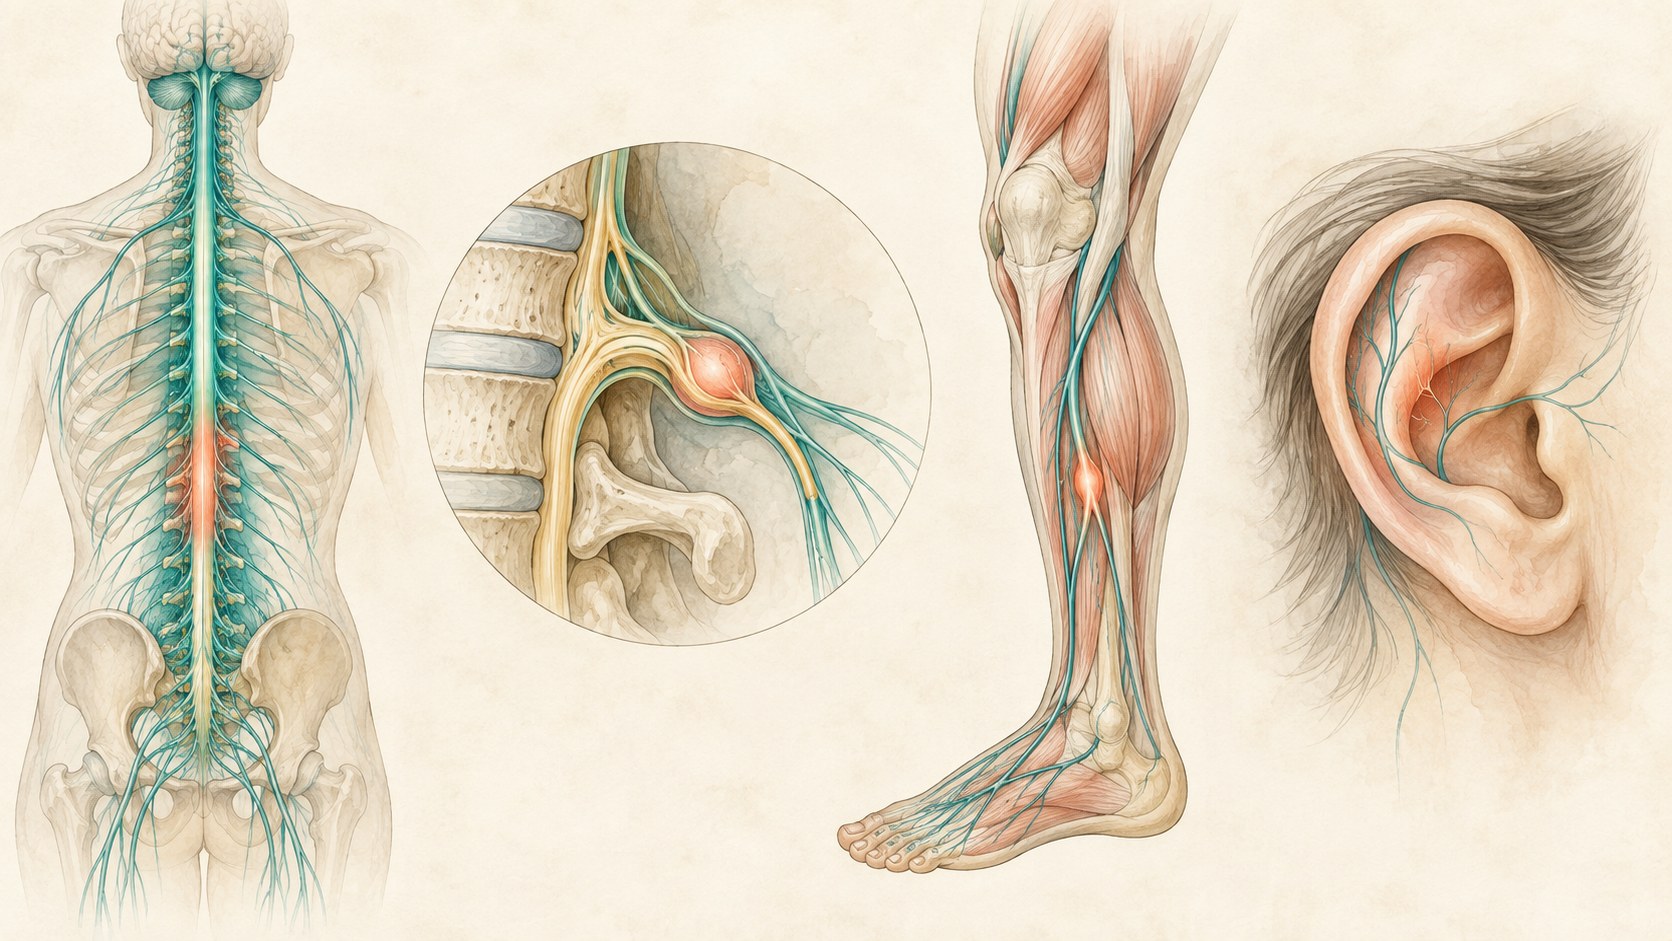
Neuromodulation is not one procedure. The target may be the spinal cord, a dorsal root ganglion, a named peripheral nerve, or superficial pathways at the ear, and each route has a different evidence base and selection process.
Quick orientation
What to know first
Implantable therapies require careful selection and may involve a temporary trial.
This guide compares options; it does not decide candidacy.
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Specific treatment
Spinal Cord Stimulation
Understand spinal cord stimulation evaluation, trial, implantation, limitations, and selection context.
Open this guideSpecific treatment
Dorsal Root Ganglion (DRG) Stimulation
Understand DRG stimulation for selected focal neuropathic pain presentations, including trial and selection context.
Open this guideSpecific treatment
Peripheral Nerve Stimulation
Understand peripheral nerve stimulation for selected named peripheral-nerve pain presentations.
Open this guideSpecific treatment
Vagus / Auricular Neuromodulation
Understand the actual nontraditional vagus/auricular neuromodulation service offered by the practice without implying implanted cervical VNS for epilepsy.
Open this guideTarget and mechanism
The target defines the modality
SCS acts near the spinal cord, DRG stimulation focuses near a sensory ganglion, and PNS is placed near a selected peripheral nerve. Auricular approaches use temporary external or percutaneous stimulation at the ear and must not be confused with implanted cervical vagus nerve stimulation.
Patient selection
Selection questions
These questions help determine whether the proposed neural target and treatment plan fit the individual problem.
SCS: selected chronic neuropathic pain patterns after diagnosis and prior care review
DRG stimulation: selected focal lower-limb CRPS or causalgia patterns within the approved indication
PNS: selected pain mapped to a specific peripheral nerve
Auricular neuromodulation: an emerging, non-equivalent pathway with protocol-specific and limited evidence
A staged decision
How the pathways differ
The pathway can range from a temporary external ear device to a percutaneous peripheral lead or a trial followed by an implanted SCS or DRG system. The device category, target, reversibility, follow-up, and evidence must be discussed separately.
Related care
Compare the four pathways
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Distinct modality
Spinal Cord Stimulation
The target is near the spinal cord, not a single peripheral nerve.
Explore this pageDistinct modality
Dorsal Root Ganglion Stimulation
The target is a selected sensory ganglion near a spinal nerve root.
Explore this pageDistinct modality
Peripheral Nerve Stimulation
PNS targets a named peripheral nerve, not the spinal cord or a dorsal root ganglion.
Explore this pageDistinct modality
Vagus / Auricular Neuromodulation
This page concerns temporary auricular stimulation, not a neck or chest implant.
Explore this pageDecision process
Decision sequence
The safest sequence starts with diagnosis and target, then compares alternatives and evidence, and only then considers a trial, temporary treatment, or implant.
Confirm the diagnosis and pain distribution
Identify the intended neural target
Compare conservative, interventional, and surgical alternatives
Discuss trial, implant, temporary treatment, and follow-up expectations
Evidence at a glance
Evidence at a glance
Evidence must be matched to the exact diagnosis, comparator, follow-up period, and system studied.
SCS evidence varies by diagnosis and comparator.
DRG has randomized comparative evidence for lower-limb CRPS and causalgia.
PNS evidence is target-specific and heterogeneous.
Auricular evidence is emerging and should not inherit claims from implanted cervical VNS.
Decision quality matters
Evidence, limits, and who it may fit
Relationship membership does not establish candidacy. Published results must be qualified by selection criteria, study design, durability, complications, and alternatives.
Risks and limits
Evidence, risks, and limits
SCS evidence varies by diagnosis and comparator. DRG has randomized comparative evidence for lower-limb CRPS and causalgia. PNS evidence is target-specific and heterogeneous. Auricular evidence is emerging and should not inherit claims from implanted cervical VNS.
No modality is universally appropriate.
A trial does not guarantee durable benefit.
Infection, lead problems, revision, explant, and loss of benefit belong in implant discussions.
Insurance authorization and device-specific details require case review.
The visit
What to expect from an evaluation
The visit should identify the diagnosis, the proposed neural target, the evidence that applies to that exact condition, alternatives, and a measurable next step.
Common questions
Neuromodulation FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is neuromodulation one treatment?
No. It is a family of approaches with different targets, devices, evidence, and risks.
Does every option require an implant?
No. Some approaches are temporary or external. SCS and DRG commonly use a trial before a permanent system is considered.
Which option is best?
There is no universal best option. The diagnosis, pain distribution, prior care, goals, contraindications, and evidence for the specific indication guide the discussion.
Target before technology
Start with a target-specific consultation
A consultation can clarify whether this modality, another treatment, or continued diagnostic work is the appropriate next step.
