
Symptoms, examination, and imaging must be interpreted together.
Spine and nerve conditions
Cervical Spinal Stenosis
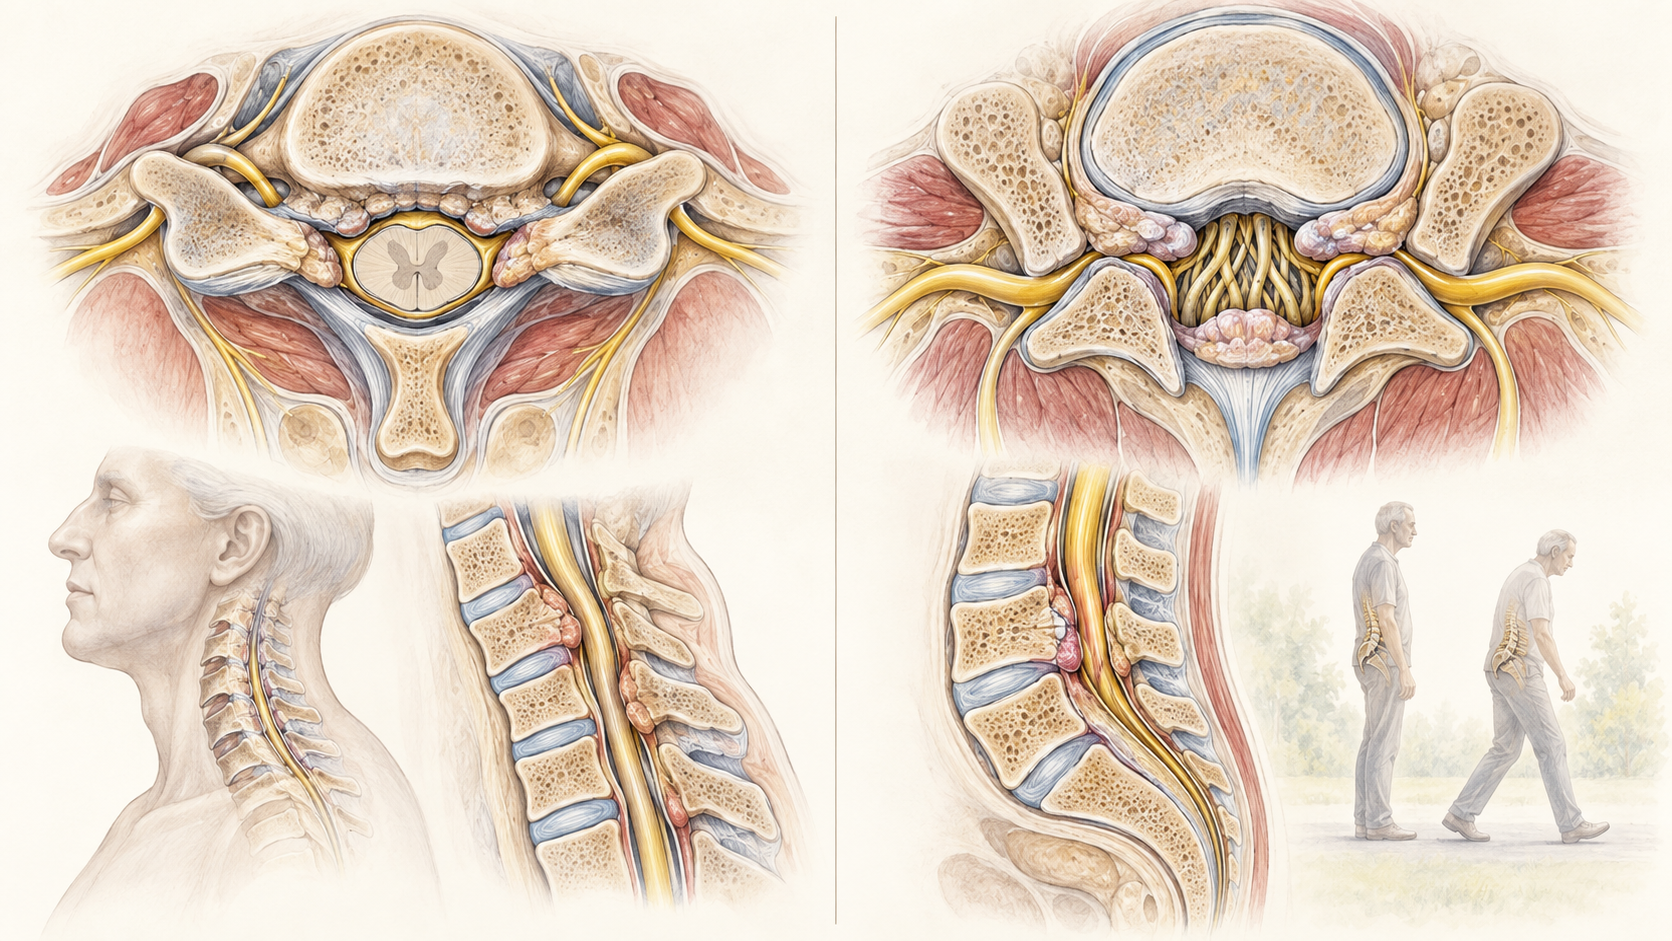
Cervical spinal stenosis means narrowing around the spinal cord in the neck. The scan finding may be asymptomatic, affect a nerve root, or contribute to spinal-cord dysfunction, and those situations require different decisions.
Quick orientation
What to know first
A scan finding can be relevant without being the entire diagnosis.
Progressive neurologic or cord-related findings can change the urgency and destination of care.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Cervical Epidural Steroid Injection
Limited to selected radicular presentations; cord/myelopathy features require safety/referral evaluation and are not an injection indication.
Symptoms are clues, not a diagnosis
What the pattern can feel like
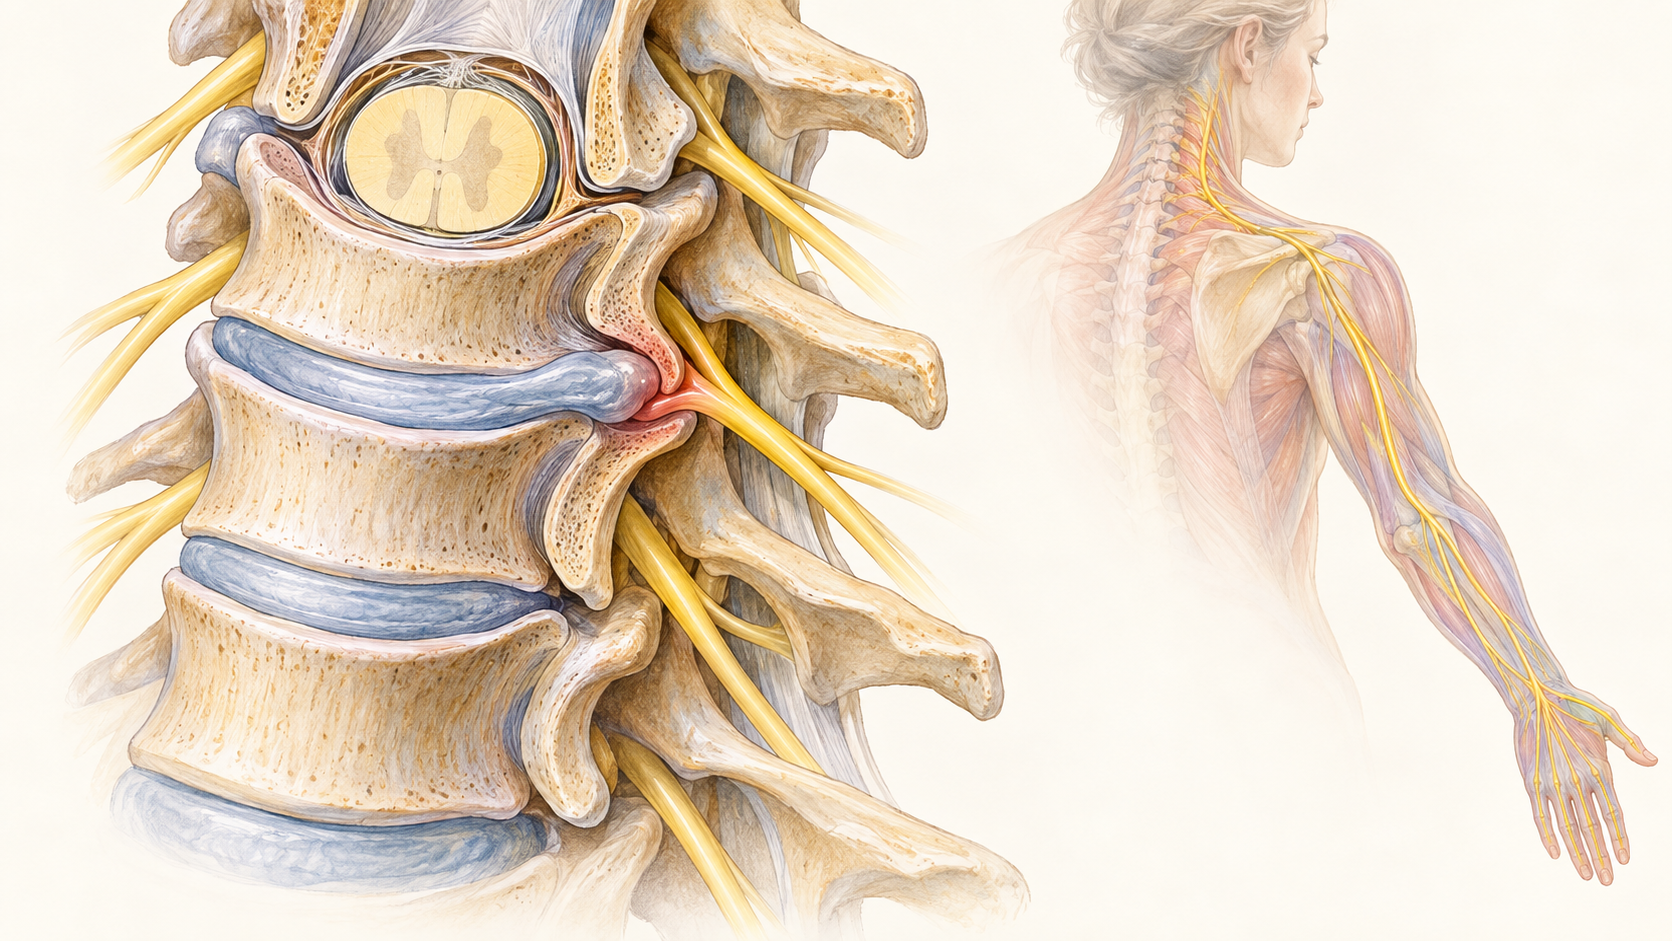
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Pain may be only one part of the pattern.
Numbness, tingling, weakness, balance, walking tolerance, and function help define the problem.
Symptoms can overlap with more than one spinal and non-spinal condition.
Relevant anatomy
Anatomy and pain mechanisms
The cervical canal contains the spinal cord, while nerve roots exit to the arms. Narrowing can arise from discs, joints, ligaments, or congenital anatomy. Cord compression with clinical myelopathy is a different safety problem from isolated radicular pain.
History and examination first
How the diagnosis is evaluated
Evaluation begins with the time course, symptom distribution, neurologic examination, functional effects, and urgent features. Imaging can identify anatomy and important alternatives, but the result must correlate with the clinical pattern.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Axial neck or low-back pain without radiculopathy
Peripheral nerve, joint, vascular, or other non-spinal sources
Facet, disc, stenosis, or nerve-root disorders with overlapping features
Infection, fracture, tumor, inflammatory disease, or another urgent cause when the history suggests it
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education and paced movement
Exercise or physical therapy tailored to the diagnosis
Medication review and risk reduction
Reassessment for changing neurologic findings or function
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Canal narrowing on imaging does not establish symptoms or myelopathy by itself.
Clinical myelopathy is identified from symptoms and examination in the setting of cord compression.
An epidural injection may be discussed only for selected radicular symptoms; it does not treat spinal-cord dysfunction.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
New hand clumsiness or loss of dexterity
New gait imbalance, falls, leg stiffness, or broad weakness
New bowel or bladder dysfunction or rapidly progressive neurologic change
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Confirm the symptom pattern and neurologic examination
Review imaging only in the context of symptoms and examination
Choose among rehabilitation, medication, watchful reassessment, procedure discussion, or referral based on the complete picture
Common questions
Cervical Spinal Stenosis FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is cervical stenosis always dangerous?
No. Severity and clinical meaning depend on symptoms, examination, cord findings, and progression.
Can an epidural injection treat myelopathy?
No. Cord-related symptoms require referral-aware assessment rather than a pain-injection pathway.
What symptoms suggest spinal-cord involvement?
Hand clumsiness, balance change, gait difficulty, broad weakness, or bowel and bladder change can be warning features.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
