
Pain location alone does not establish the diagnosis.
Abdominal, pelvic, groin, chest wall and rib conditions
Ilioinguinal / Iliohypogastric Neuralgia
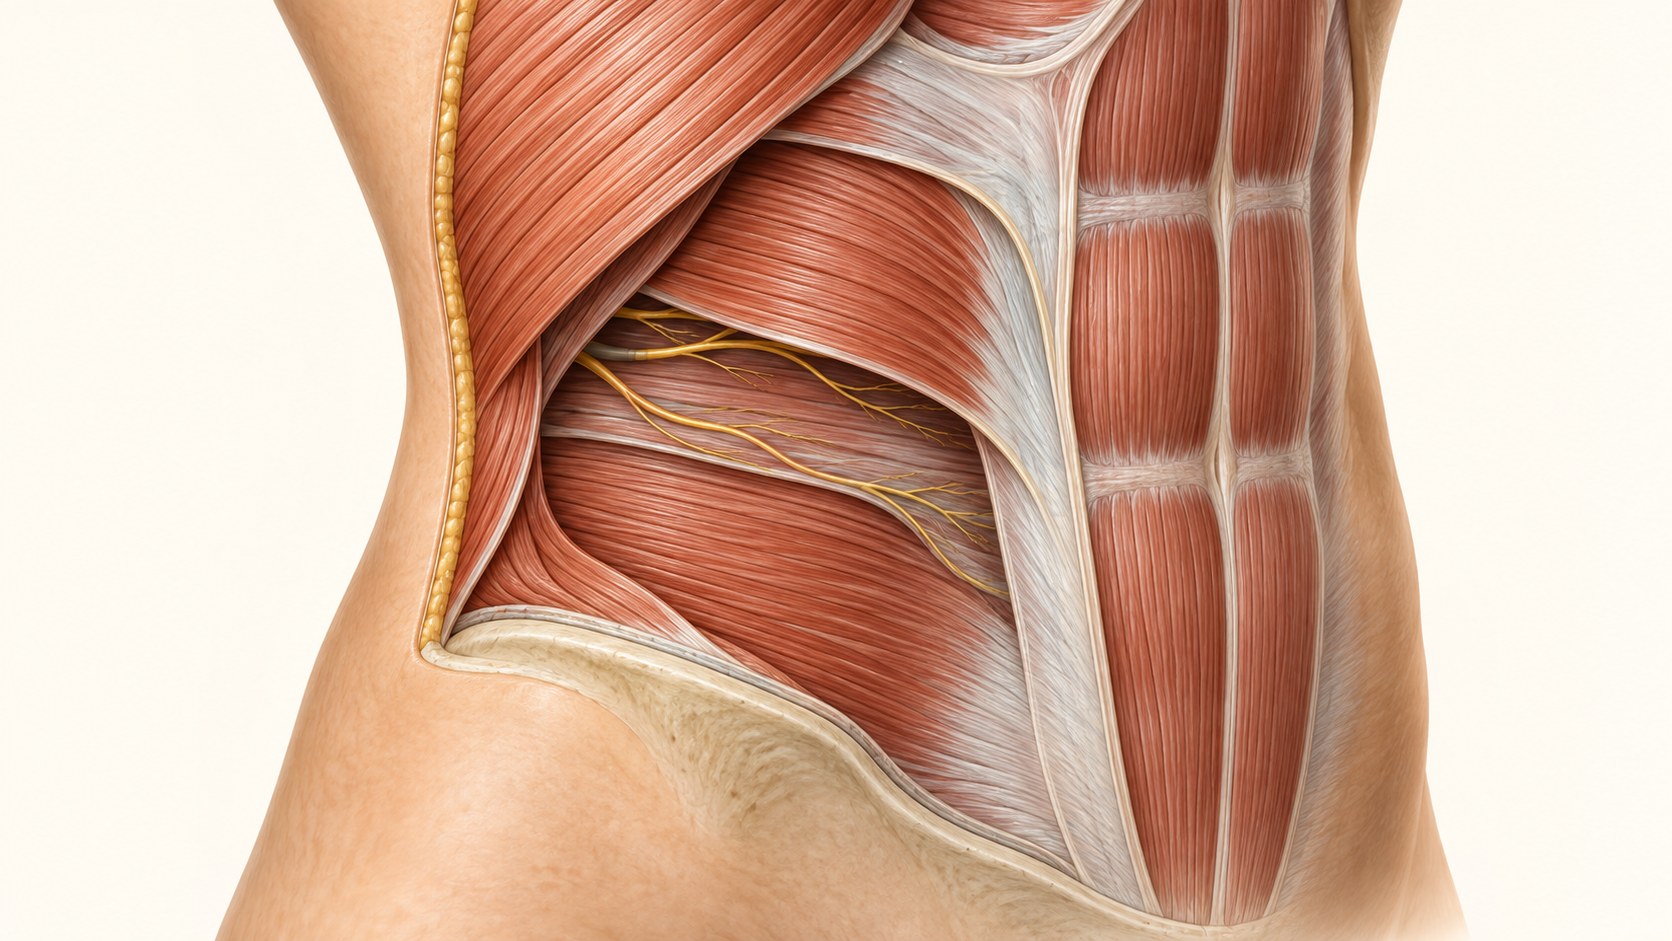
Ilioinguinal / Iliohypogastric Neuralgia describes pain suspected to involve the ilioinguinal or iliohypogastric nerve. Symptoms may follow a recognizable distribution, but anatomy varies and nearby nerve, organ, abdominal-wall, pelvic-floor, hip, spine, and postsurgical causes can overlap.
Quick orientation
What to know first
Visceral, musculoskeletal, spinal, hip, pelvic-floor, neuropathic, postsurgical, infectious, vascular, and oncologic causes can overlap.
Red flags and the likely organ or tissue source can change the timing and destination of care.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Ilioinguinal Nerve Block
Target-specific block may help distinguish an ilioinguinal contribution.
Diagnostic / prognostic step
Iliohypogastric Nerve Block
Target-specific block may help distinguish an iliohypogastric contribution.
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Care overview
Nerve Pain
Orientation to neuropathic symptoms and named diagnoses without becoming a catch-all diagnosis page.
Open this guideClinical guide
Peripheral Neuropathy
Peripheral neuropathy symptoms, cause-oriented evaluation, safety considerations, and treatment pathways.
Open this guideClinical guide
Painful Diabetic Neuropathy
Painful diabetic peripheral neuropathy, evaluation, risk-aware management, and treatment pathways.
Open this guideClinical guide
Complex Regional Pain Syndrome
CRPS symptoms, diagnostic complexity, multidisciplinary care, and appropriate treatment pathways.
Open this guideClinical guide
Occipital Neuralgia
Occipital neuralgia symptoms, diagnosis, differential considerations, and relevant treatment pathways.
Open this guideClinical guide
Intercostal Neuralgia
Named intercostal-nerve pain, its differential diagnosis, evaluation, and treatment pathways.
Open this guideClinical guide
Pudendal Neuralgia
Pudendal-distribution pain, evaluation, referral boundaries, and treatment pathways.
Open this guideClinical guide
Genitofemoral Neuralgia
Genitofemoral-distribution pain, differential diagnosis, and treatment pathways.
Open this guideSymptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Distribution, timing, quality, sensory change, posture, movement, coughing, meals, bowel or bladder symptoms, and prior surgery help define the pattern.
Named nerve territories overlap and vary; tenderness or pain in a territory does not by itself prove neuralgia.
Function, sleep, trauma, infection, systemic disease, and progression shape the evaluation.
Relevant anatomy
Anatomy and pain mechanisms
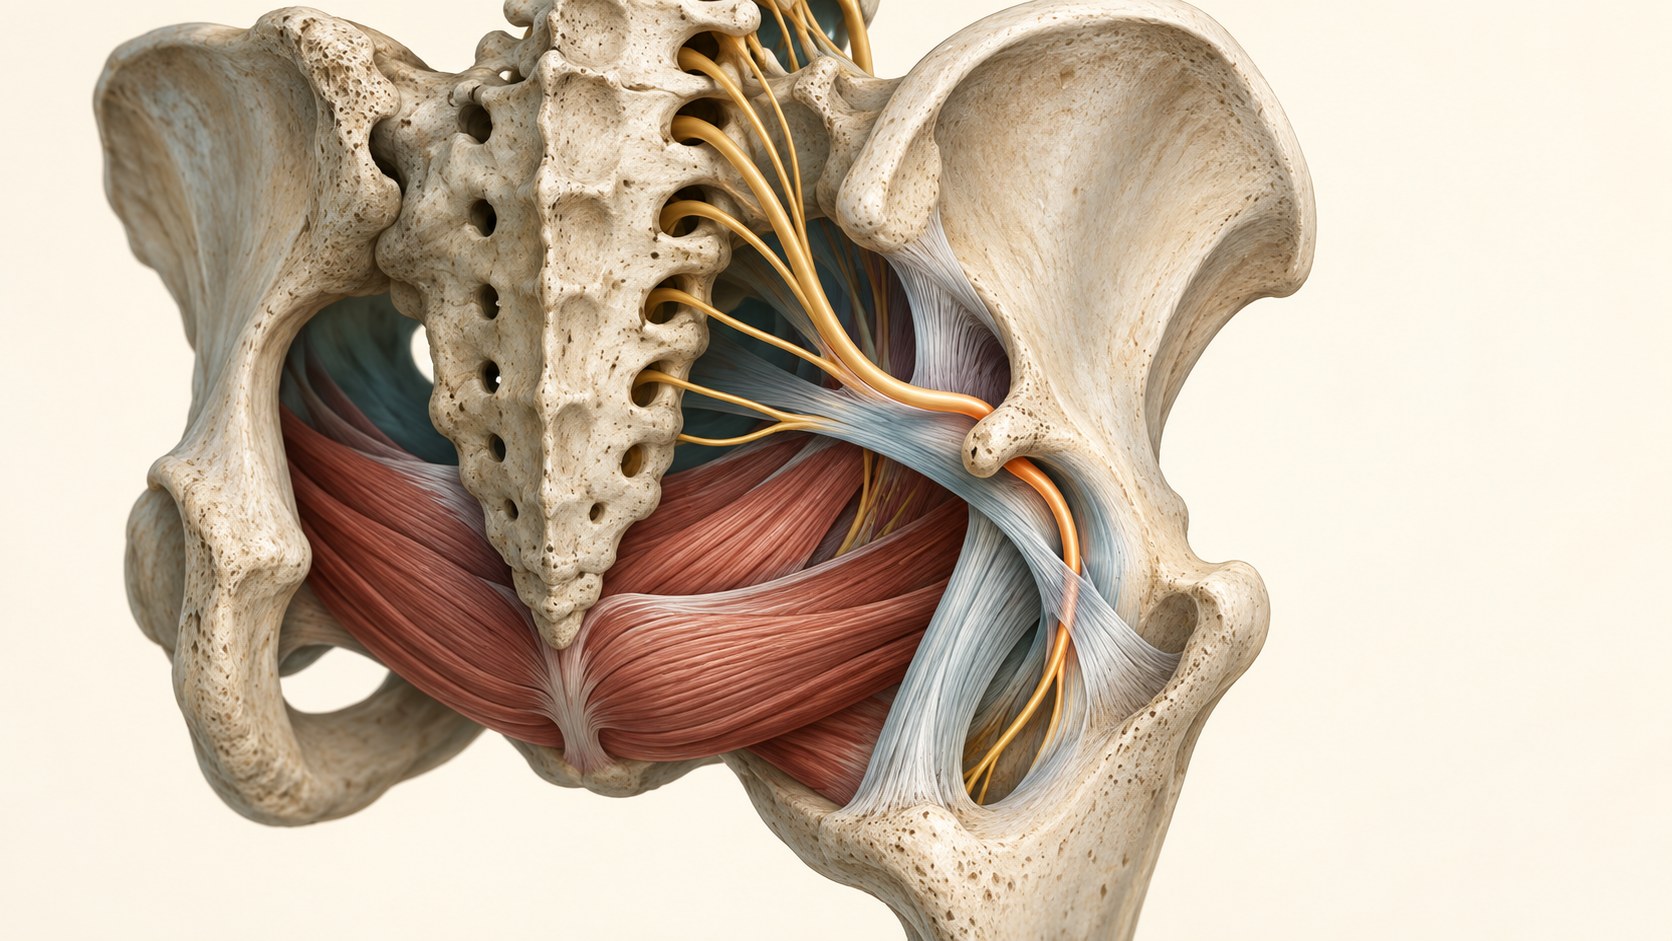
The ilioinguinal or iliohypogastric nerve has a defined but variable course through the lower abdominal wall, incision region, groin, and adjacent sensory territory. Neighboring sensory territories overlap, so symptom location, tenderness, or temporary block response cannot establish the diagnosis alone.
History and examination first
How the diagnosis is evaluated
Evaluation starts by separating urgent and visceral causes from abdominal-wall, pelvic-floor, hip, spine, musculoskeletal, and named-nerve patterns. Examination and selective testing are matched to the clinical question. A temporary block response can add information but does not independently prove the diagnosis.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Genitofemoral neuralgia or overlapping postoperative neuropathy
Hernia, abdominal-wall pain, hip disorder, lumbar radiculopathy, or visceral cause
Visceral, hernia, pelvic-floor, hip, spine, abdominal-wall, infectious, vascular, traumatic, or oncologic causes
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education and activity changes matched to the suspected diagnosis
Medication review with the appropriate clinician
Physical or pelvic-floor rehabilitation when the evaluation supports it
Reassessment when symptoms, neurologic findings, function, or treatment response change
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Ilioinguinal and iliohypogastric territories overlap and anatomic variation is common.
Published block evidence is heterogeneous and does not establish diagnosis from response alone.
Postsurgical pain can have scar, mesh, muscle, hernia, and neuropathic contributors.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
New severe pelvic or abdominal pain with fainting, heavy bleeding, pregnancy concern, fever, or persistent vomiting
New bowel or bladder dysfunction, saddle sensory loss, progressive weakness, or rapidly worsening neurologic symptoms
A new mass, unexplained weight loss, major trauma, visible blood, or symptoms suggesting infection, vascular disease, or cancer
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the exact distribution, timing, triggers, sensory features, prior surgery or trauma, and functional effect
Examine the abdomen, pelvis, groin, spine, hip, chest wall, skin, neurologic system, or pelvic floor as the presentation requires
Use imaging, laboratory testing, specialist referral, or a focused diagnostic procedure selectively
Choose conservative care, further diagnostic work, a target-specific treatment discussion, or referral without assuming a fixed sequence
Common questions
Ilioinguinal / Iliohypogastric Neuralgia FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Does pain in the area associated with Ilioinguinal / Iliohypogastric Neuralgia prove neuralgia?
No. Named nerve territories overlap and other organ, wall, joint, spine, pelvic-floor, and postsurgical causes can produce a similar pattern.
Can a helpful nerve block confirm Ilioinguinal / Iliohypogastric Neuralgia?
No. A temporary response is interpreted with the full history, examination, alternatives, and technical context.
Is radiofrequency an automatic next step for Ilioinguinal / Iliohypogastric Neuralgia?
No. Diagnosis, target confidence, evidence, risks, alternatives, and goals require a separate review.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
