
Symptoms, examination, function, and imaging must be interpreted together.
Joint and musculoskeletal conditions
Myofascial Pain Syndrome
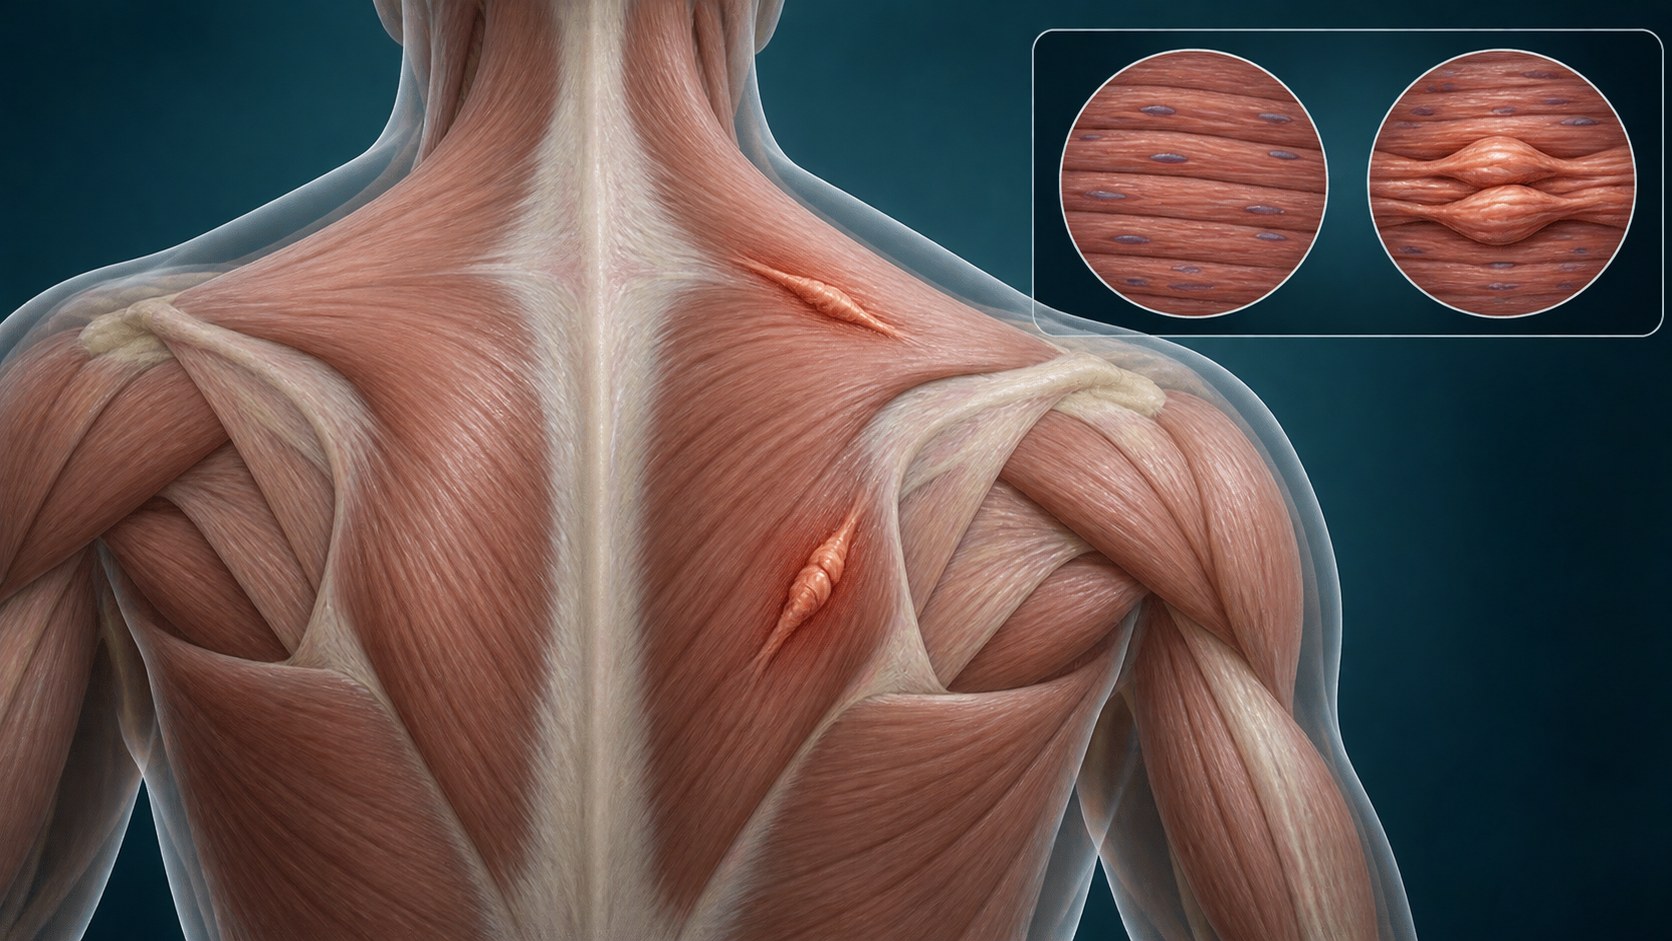
Myofascial pain describes pain associated with muscle and surrounding connective tissue. A tender or taut area can be clinically useful, but it should not end the search for joint, nerve, spine, systemic, or other causes.
Quick orientation
What to know first
Neighboring joints, tendons, nerves, and referred pain can overlap.
A procedure is one possible tool, not proof of the diagnosis or an automatic next step.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Options that may be considered
These are options, not required steps. Selection depends on the diagnosis and individual review.
Treatment option
Trigger Point Injection
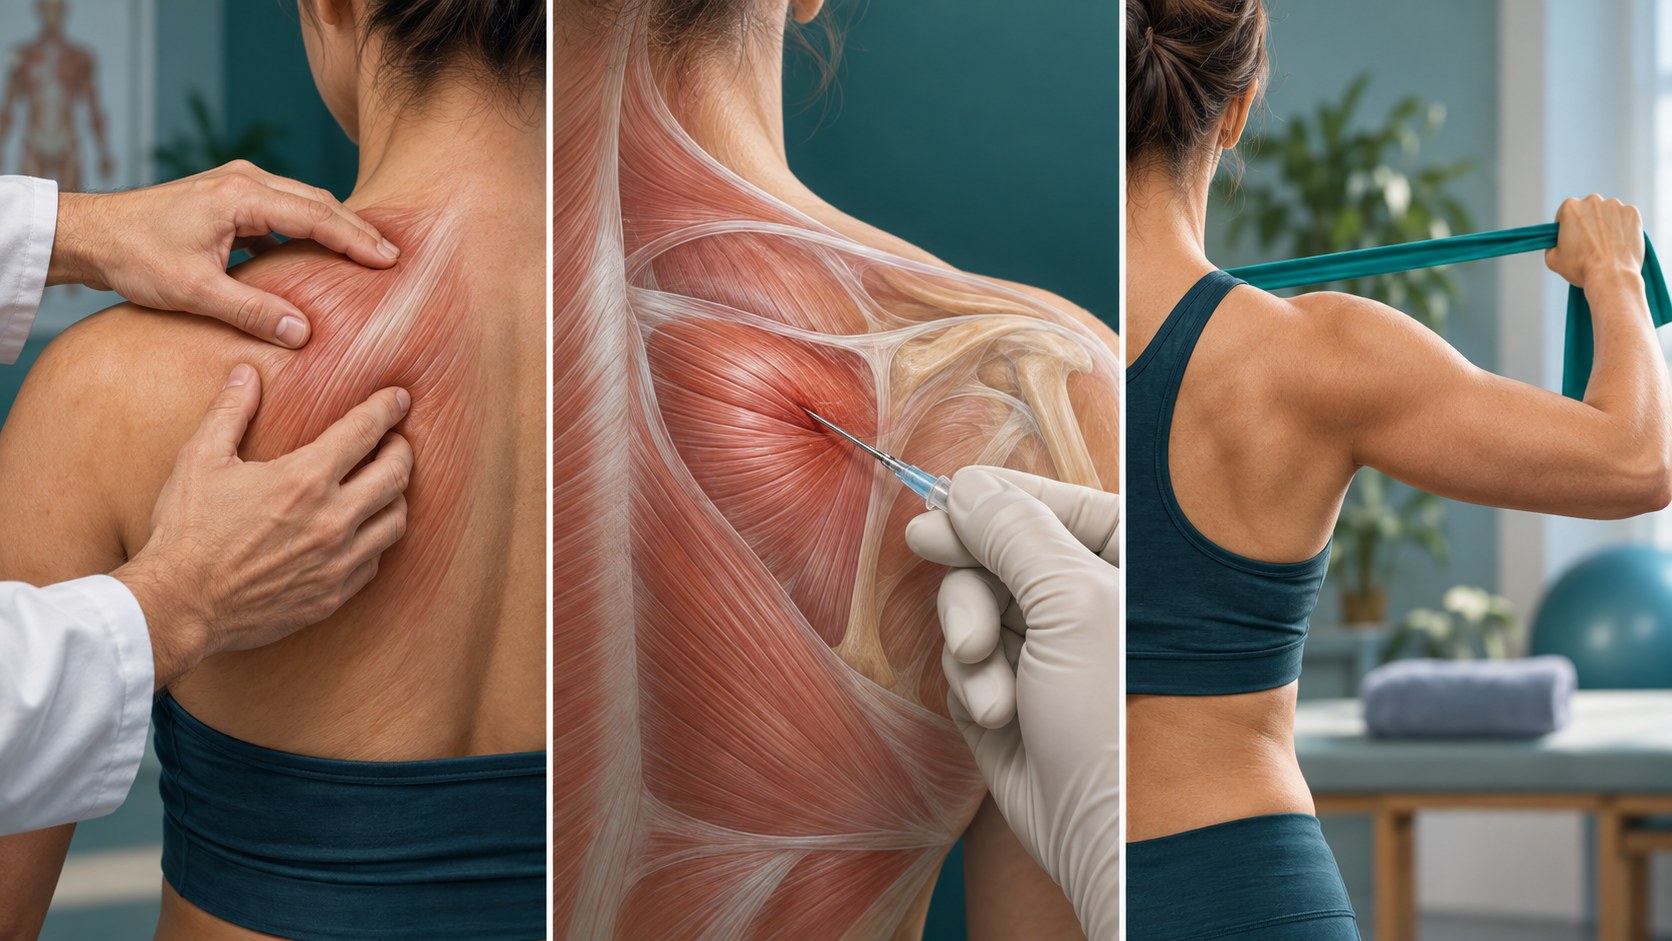
May be considered as one component of a broader rehabilitation-oriented myofascial treatment plan.
Symptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Pain location and movement sensitivity can narrow the differential but rarely identify one structure alone.
Stiffness, range of motion, loading tolerance, weakness, swelling, and daily function add diagnostic context.
The pattern should be checked for referred pain, neurologic features, inflammatory disease, injury, and other alternatives.
Relevant anatomy
Anatomy and pain mechanisms
Muscle pain can involve localized tenderness, altered activation, guarding, and sensitivity within a broader movement and health context. Trigger points are examination findings, and their definition and reliability vary across studies and clinicians.
History and examination first
How the diagnosis is evaluated
Evaluation combines the history, movement and loading pattern, focused examination, functional goals, and selective imaging. Structural change can support a diagnosis, but imaging severity and symptom severity may not match.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Referred spinal or nerve-related pain
Tendon, bursa, muscle, or neighboring joint disorders
Inflammatory arthritis, infection, fracture, or another less common cause when the history suggests it
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, and movement matched to irritability
Progressive strength, mobility, and function when appropriate
Medication review that accounts for individual risks
Reassessment when the pattern changes or improvement stalls
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Trigger-point definitions, patient groups, injectates, and outcomes vary substantially across studies.
Some acute-care trials favor injection over medical management, but the evidence base is small and heterogeneous.
Chronic neck and back evidence does not establish one injectate or technique as uniformly superior.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
Fever, a hot swollen joint, or systemic illness
Major trauma or inability to bear weight or use the limb
Rapidly progressive weakness, numbness, or a new emergency symptom pattern
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the symptom pattern and meaningful functional limits
Examine the joint and neighboring regions before attributing symptoms to one structure
Review imaging only in clinical context
Choose among rehabilitation, medication review, a selected procedure discussion, or referral without assuming a fixed sequence
Common questions
Myofascial Pain Syndrome FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is every muscle knot a trigger point?
No. Tenderness is common, and a broader evaluation is needed before assigning a myofascial diagnosis.
Can myofascial pain overlap with joint or nerve pain?
Yes. Overlap is common and may change which treatment is useful.
Are injections the main treatment?
Not necessarily. Movement, rehabilitation, sleep, workload, and other contributors often remain central to care.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
