
Peripheral neuropathy, radiculopathy, and focal entrapment are different clinical problems.
Peripheral nerve and neuropathy conditions
Tarsal Tunnel Syndrome
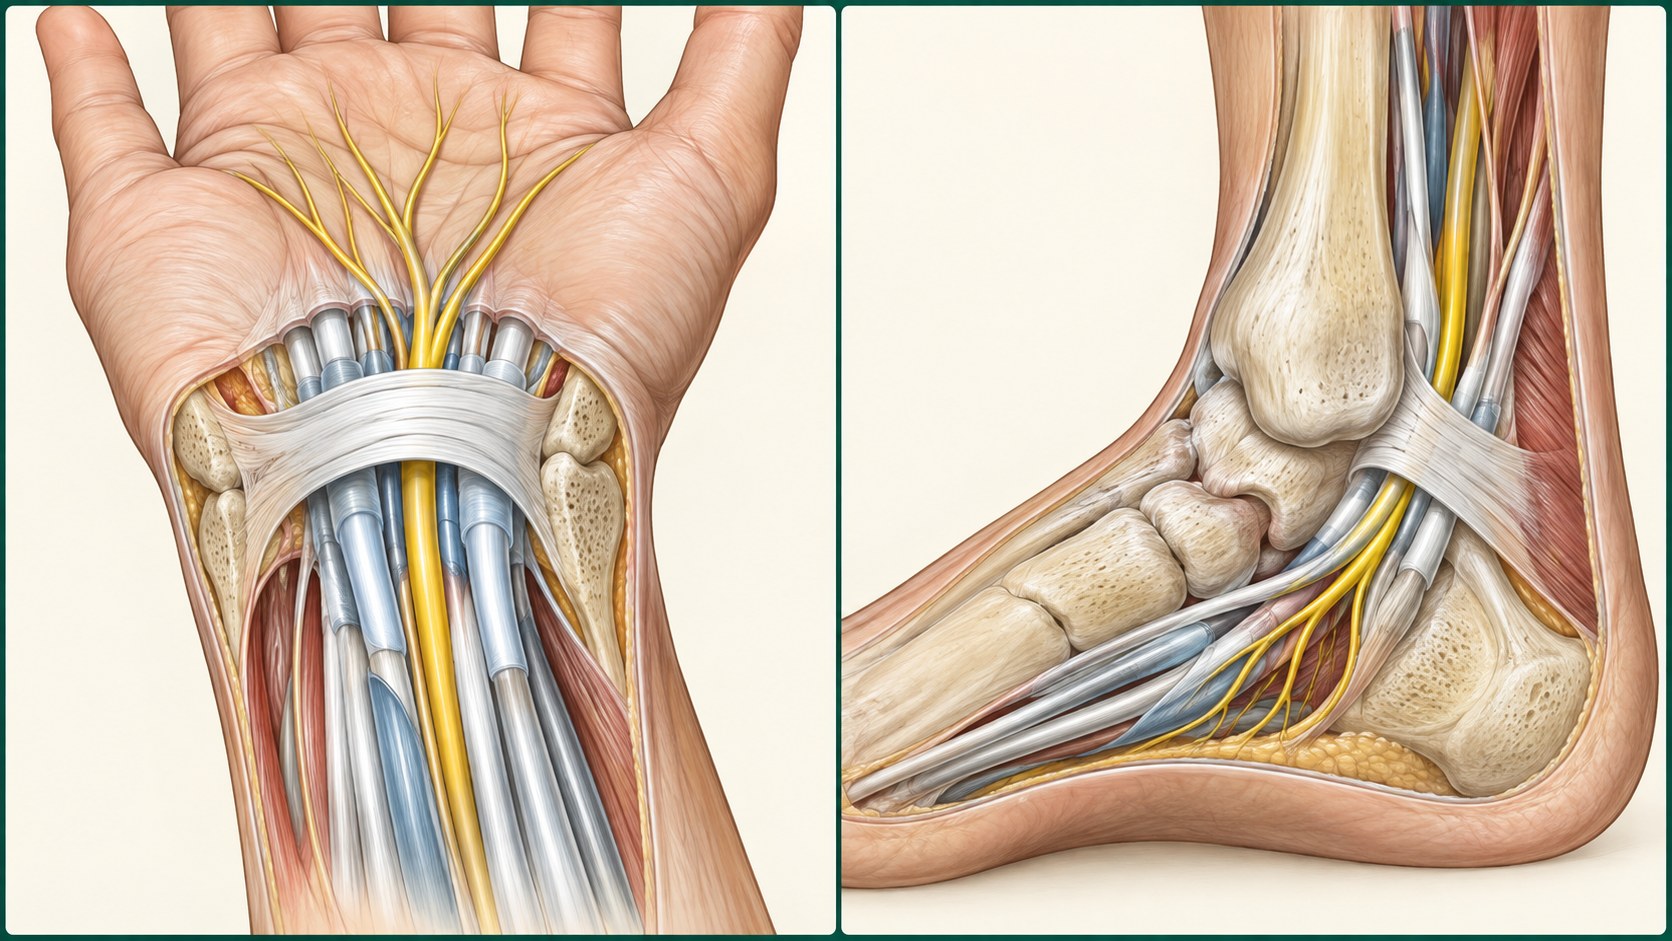
Tarsal tunnel syndrome describes tibial nerve compression near the inner ankle. Burning or tingling in the foot can have many causes, and current research shows substantial variation in how this diagnosis is established.
Quick orientation
What to know first
Symptoms may overlap, so distribution alone does not prove one diagnosis.
Evaluation should look for the cause, neurologic deficits, and conditions that need different care.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Tibial Nerve Block
May contribute to a diagnostic pathway when focal tibial nerve entrapment at the tarsal tunnel is clinically suspected.
Diagnostic / prognostic step
Ankle Peripheral Nerve Block
May contribute to a target-specific diagnostic pathway for Tarsal Tunnel Syndrome; broad Ankle Pain and Foot Pain route through diagnosis rather than receiving a generic direct edge.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Tibial Nerve Radiofrequency Treatment
May be considered only within a reviewed sequence after diagnosis and response to less durable diagnostic or therapeutic steps; this edge does not establish routine use.
Symptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Numbness, tingling, burning, altered sensation, or weakness can occur, but the pattern matters.
Diffuse symptoms in both feet or hands differ from one named-nerve territory or a spinal root pattern.
Function, balance, grip, gait, sleep, and progression help define urgency and next testing.
Relevant anatomy
Anatomy and pain mechanisms
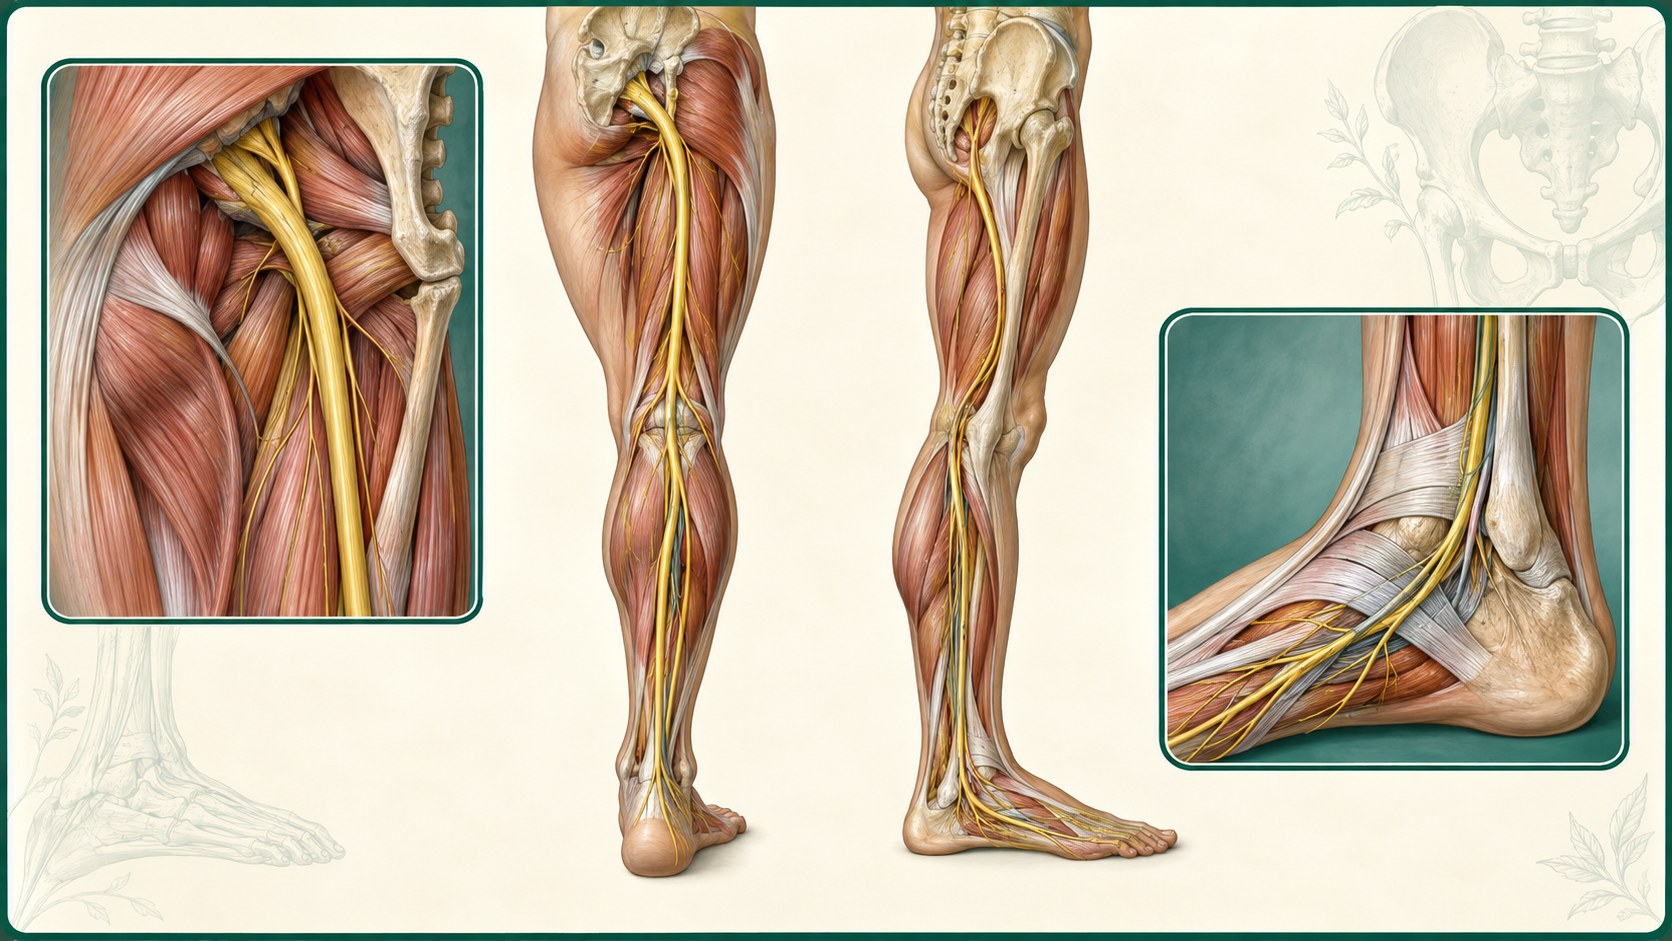
The tibial nerve travels behind the medial ankle through a confined tunnel before dividing toward the foot. Tendon, vessel, bone, soft-tissue, and variant anatomy can affect the region, while polyneuropathy and radiculopathy can produce overlapping symptoms.
History and examination first
How the diagnosis is evaluated
Evaluation combines the history, neurologic and musculoskeletal examination, medical risk review, and selective testing. Electrodiagnostic studies, imaging, ultrasound, or laboratory tests can add information, but no single result replaces clinical correlation.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Radiculopathy or spinal cord disease
Focal entrapment versus diffuse polyneuropathy
Joint, tendon, vascular, inflammatory, metabolic, toxic, hereditary, or medication-related causes
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education and protection of vulnerable skin or joints
Activity, therapy, and assistive strategies matched to deficits
Medical evaluation for reversible or treatable contributors
Reassessment when weakness, balance, distribution, or function changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
There is no accepted single gold-standard test for tarsal tunnel syndrome.
Provocative tests, electrodiagnostic findings, and ultrasound measurements show variable performance across studies.
Treatment evidence is heterogeneous, and selection should account for cause, severity, alternatives, and surgical considerations.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
A cold, pale, blue, rapidly swollen, or suddenly painful foot, loss of pulse, or new inability to move the foot
A hot red foot, fever, spreading redness, open wound, drainage, or another concern for infection
Rapidly progressive weakness, loss of sensation, major trauma, deformity, or inability to bear weight
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the symptom distribution, timing, and functional effect
Examine strength, sensation, reflexes, joints, spine, and named nerve pathways as appropriate
Use imaging, laboratory testing, or electrodiagnostic studies selectively
Choose conservative care, a target-specific procedure discussion, or referral without assuming a fixed sequence
Common questions
Tarsal Tunnel Syndrome FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is all burning foot pain tarsal tunnel syndrome?
No. Polyneuropathy, radiculopathy, plantar disorders, vascular disease, and other causes can overlap.
Does a normal nerve test exclude it?
Not always. Test sensitivity varies, so results must be interpreted with the full clinical pattern.
Does a helpful block prove the diagnosis?
No. A response may add information but is not definitive by itself.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
