
The diagnosis and named anatomic target come before the procedure.
Peripheral nerve procedures
Supraclavicular Brachial Plexus Block
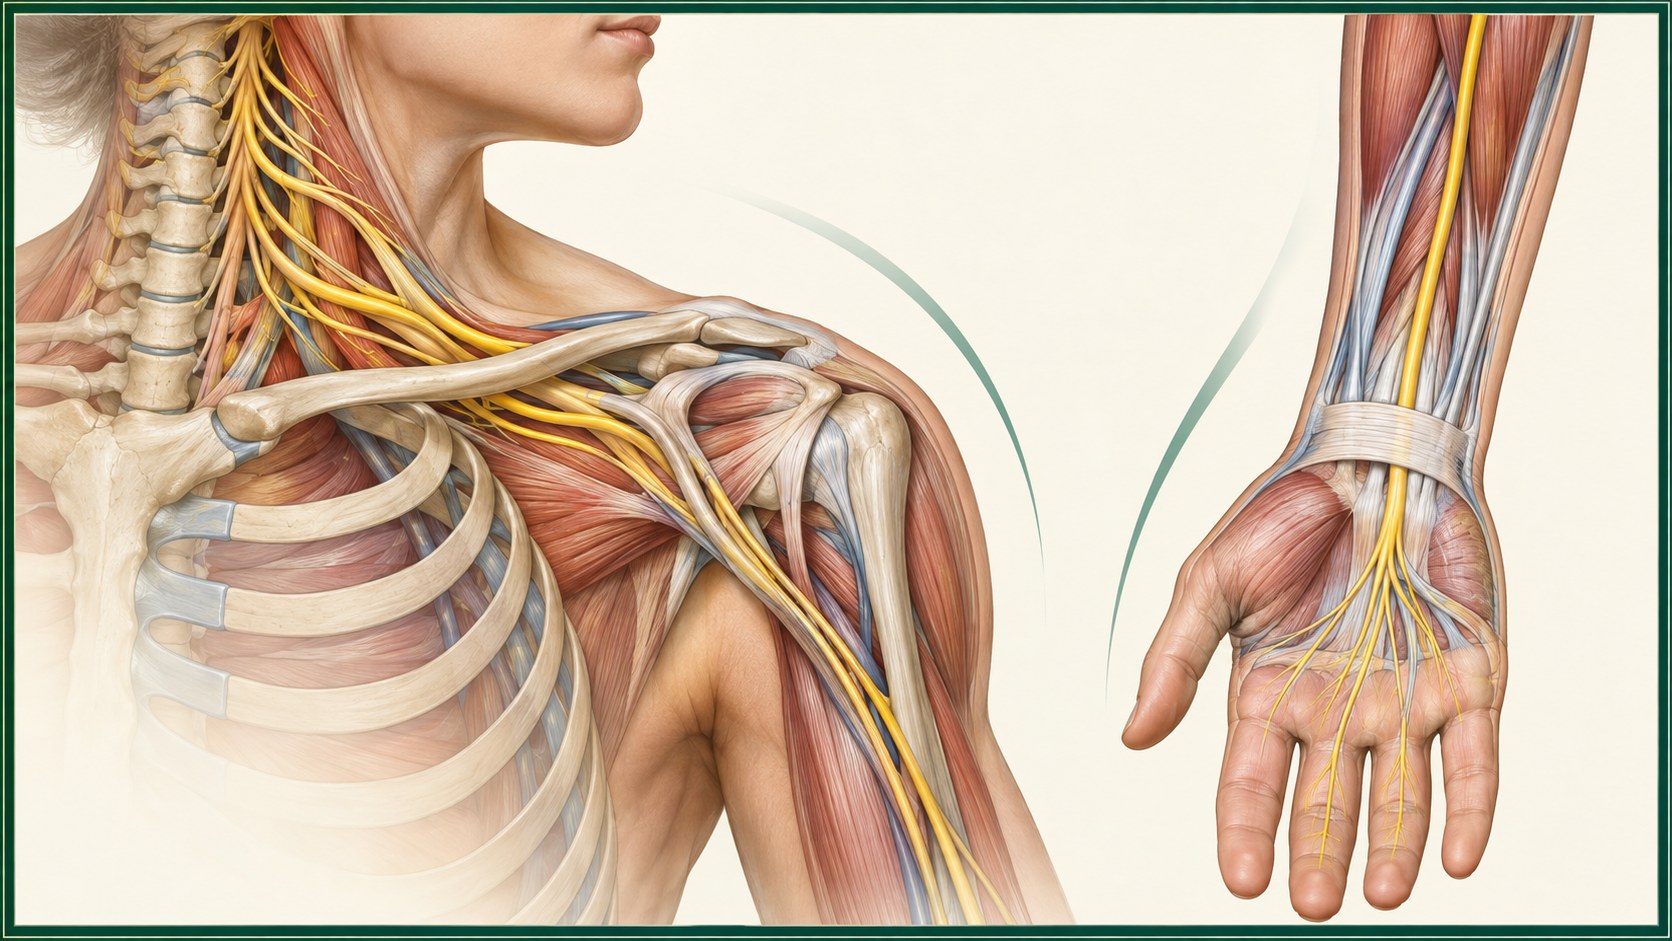
A supraclavicular brachial plexus block affects multiple upper-limb nerve pathways near the collarbone. Its broad effect and nearby lung, vessels, and nerves make diagnosis, purpose, and safety review especially important.
Quick orientation
What to know first
A nerve block, radiofrequency procedure, joint injection, and neuromodulation have different purposes.
Response to one step can inform the plan but does not prove diagnosis or require a next procedure.
Target and mechanism
The target defines the procedure
The brachial plexus is compact above the clavicle near the subclavian vessels and pleura. A proximal block differs from a median, ulnar, radial, or suprascapular target and can temporarily affect broad sensory and motor function.
Patient selection
Selection questions
Selection begins with a clinically coherent diagnosis and a specific anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether a procedure is the right next decision.
A clinically coherent diagnosis and named target
Meaningful functional limitation despite appropriate initial care or a focused diagnostic question
A risk review that supports the proposed procedure
A defined goal and reassessment plan
A staged decision
How we decide what may come next
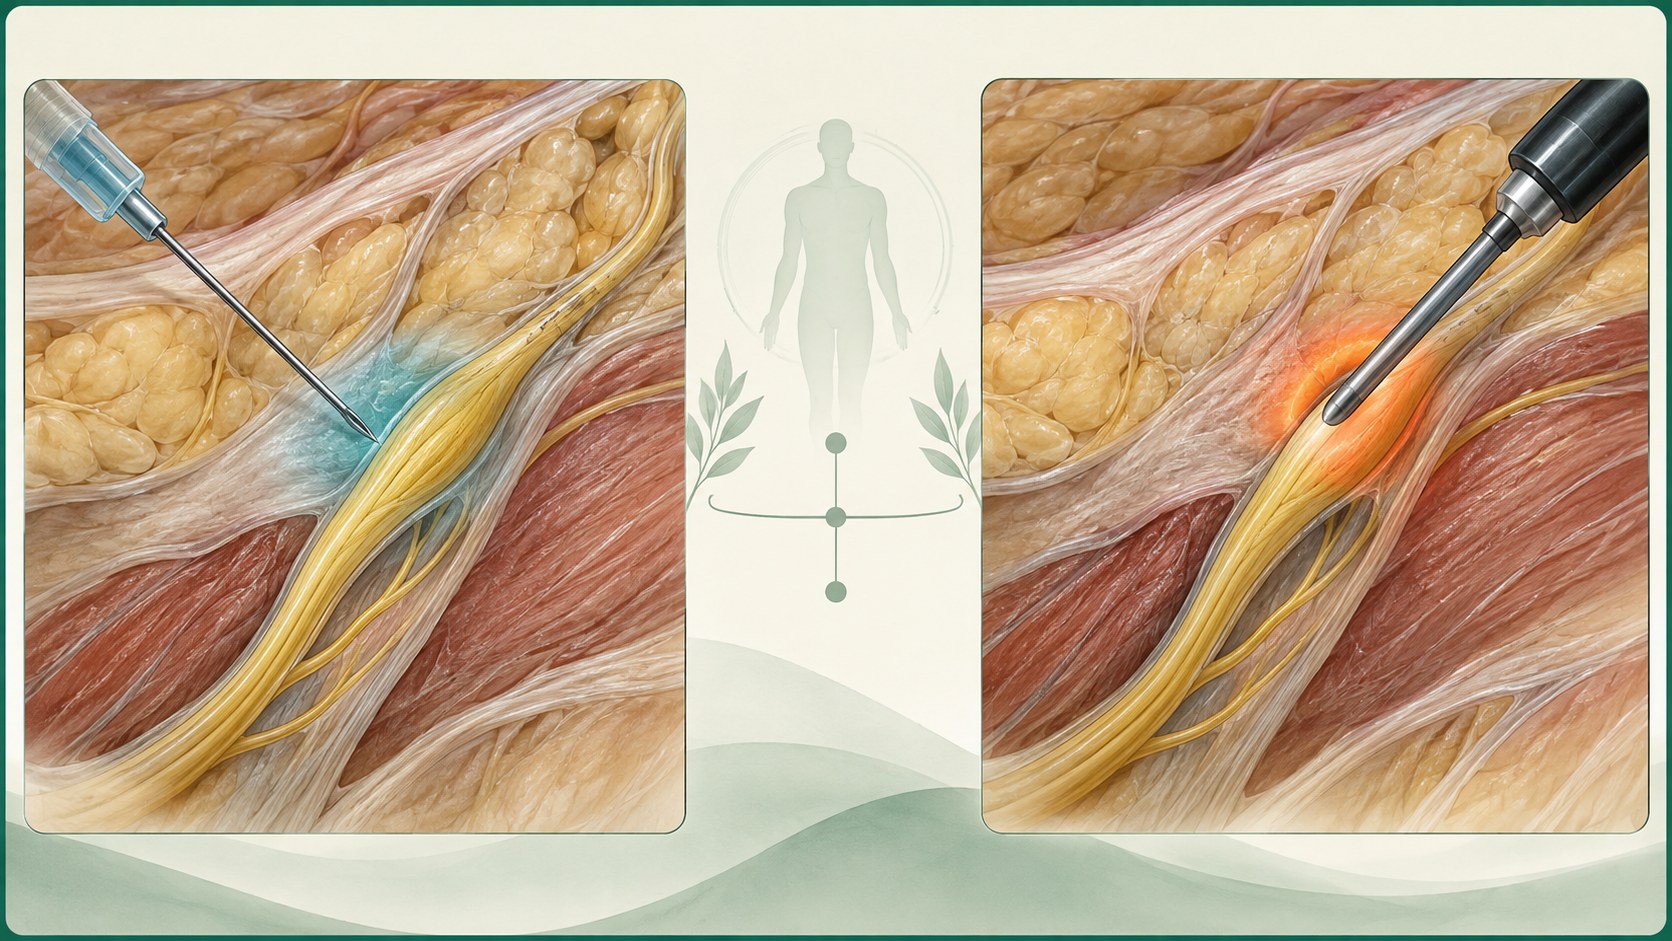
The clinician identifies the plexus and surrounding structures with ultrasound, reviews respiratory and neurologic risk, and places local anesthetic in the intended tissue plane. Chronic-pain use remains distinct from surgical anesthesia.
Related care
Conditions this treatment may be considered for
These related options are educational. They do not establish a diagnosis, candidacy, recommendation, or required treatment sequence.
Alternative
Complex Regional Pain Syndrome
Alternative consideration for selected upper-extremity CRPS presentations within multidisciplinary management; not routine, universally applicable, or applicable to lower-extremity CRPS.
Explore this pageDecision process
Decision sequence
A procedure is an optional treatment discussion, not an automatic step. The response must be reassessed against the usual symptoms and meaningful activities. A limited, absent, or discordant response should reopen the diagnosis and alternatives instead of triggering an automatic series.
Confirm the diagnosis and named target
Review alternatives, evidence quality, and medical risks
Define meaningful functional and symptom goals
Reassess the result before deciding what comes next
Evidence at a glance
Evidence at a glance
Study results depend on diagnosis, selection, comparator, technique, outcome, and follow-up.
Most high-quality brachial plexus block evidence addresses perioperative anesthesia rather than chronic pain.
A frozen relationship permits only a narrow alternative discussion for selected upper-extremity CRPS within multidisciplinary care.
Pneumothorax, vascular puncture, nerve injury, local anesthetic toxicity, and temporary weakness require explicit risk review.
Decision quality matters
Evidence, limits, and who it may fit
A listed option or imaging finding does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Evidence, risks, and limits
Most high-quality brachial plexus block evidence addresses perioperative anesthesia rather than chronic pain. A frozen relationship permits only a narrow alternative discussion for selected upper-extremity CRPS within multidisciplinary care. Pneumothorax, vascular puncture, nerve injury, local anesthetic toxicity, and temporary weakness require explicit risk review.
Bleeding, infection, temporary numbness or weakness, nerve injury, local anesthetic toxicity, allergic or medication effects, and target-specific injury require individualized consent.
Medication, volume, target approach, sedation, medication holds, driving, activity, and follow-up are individualized.
A procedure does not replace evaluation of progressive neurologic loss, urgent disease, or a surgical problem.
The visit
What to expect from a consultation
The visit should define the diagnosis, intended target, evidence, alternatives, risks, and the next useful decision. Medication, frequency, sedation, medication holds, driving, and aftercare remain individualized clinician decisions.
Common questions
Supraclavicular Brachial Plexus Block FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is this a block for all arm pain?
No. It has a broad proximal effect and only fits a specific diagnostic and treatment purpose.
Is it the same as a wrist nerve injection?
No. It targets the plexus near the collarbone rather than one distal nerve.
Can it affect breathing or strength?
Depending on anatomy and spread, respiratory or motor effects can occur and require individualized review.
Question before procedure
Start with a diagnosis-first consultation
A consultation can clarify whether a selected procedure, another treatment, continued conservative care, or referral fits the clinical picture.
