
Key Takeaways
- Facet changes on imaging do not, by themselves, prove that a facet joint is the source of pain.
- Medial branch blocks are commonly used as prognostic tests before lumbar facet radiofrequency ablation.
- Benefit is not assured and the treated nerves can recover over time; repeat treatment is an individualized decision.
- Selection standards, block thresholds, technique, and repeat-procedure policies vary and should be discussed directly.
The diagnostic problem comes first
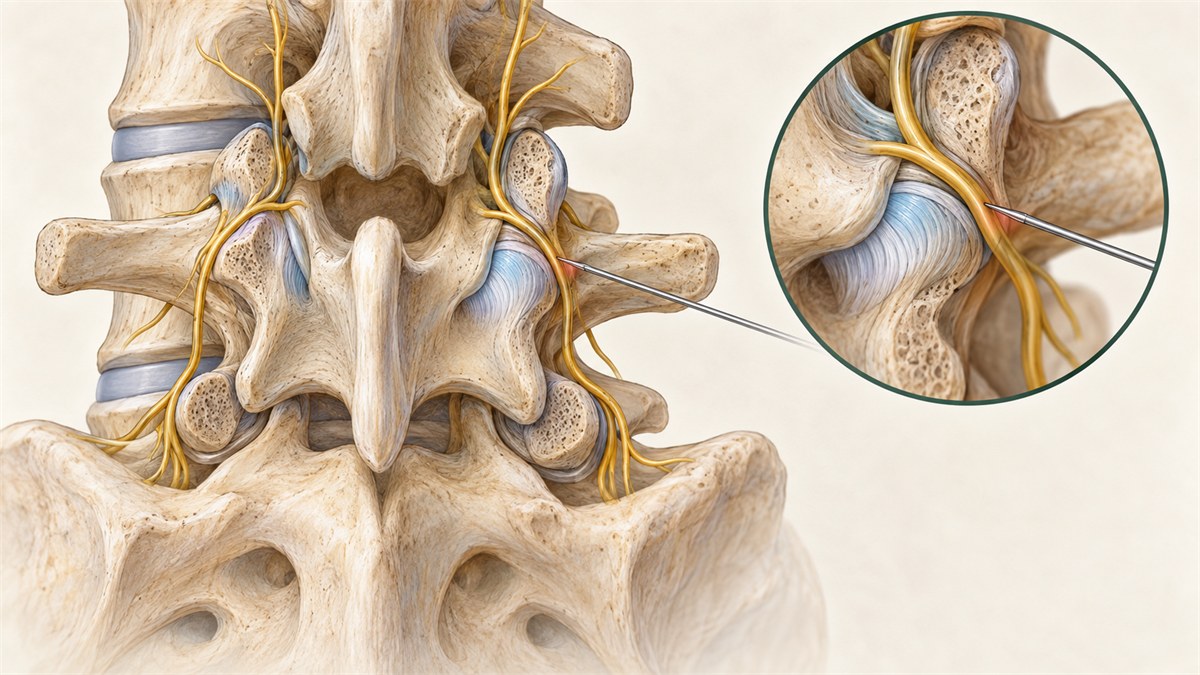
Facet joints are paired joints at the back of the spine. Small medial branch nerves transmit sensory information from them. Pain patterns, examination findings, and imaging may raise suspicion, but no single history, physical finding, or scan establishes facet-mediated pain with certainty.
That uncertainty explains the staged pathway. A clinician may first recommend conservative care and then, when appropriate, perform a carefully controlled medial branch block. Temporary, meaningful improvement that matches the anesthetic window can add evidence that interrupting the same nerve pathway may be useful.

How lumbar radiofrequency ablation works
During lumbar radiofrequency ablation, an electrode is positioned near a target medial branch nerve using image guidance. Radiofrequency energy creates a controlled thermal lesion intended to interrupt pain transmission from the joint. Electrode orientation, imaging, stimulation practices, lesion parameters, and lumbar anatomy all influence technique.
The treatment does not remove arthritis, realign the spine, strengthen supporting muscles, or identify every contributor to lower-back pain. It is a targeted intervention within a broader plan.
Who may be considered
A potential candidate generally has persistent axial lower-back pain, a clinical picture compatible with lumbar facet-mediated pain, and an appropriate response to prognostic blocks. The exact number of blocks and the response threshold remain debated; guidelines acknowledge tradeoffs between stricter selection and false-negative results.
The decision also considers alternative diagnoses, prior treatment, medications, infection and bleeding risks, neurologic findings, patient goals, and whether the anticipated functional gain justifies the procedure. This article does not extend lumbar evidence to cervical treatment decisions.
What to expect from the conversation
Ask which joints and nerves are being targeted, what the diagnostic block showed, how the clinician defines a positive response, what outcome is realistic, and how progress will be measured. Discuss procedure-day medication instructions, temporary soreness or numbness, uncommon complications, and what symptoms require urgent contact.
Relief may be incomplete or absent. When benefit later fades, that does not automatically mean repeating the procedure is appropriate; the diagnosis, duration and quality of benefit, interval health changes, and alternatives should be revisited.
Evidence context
The evidence base supports possible benefit in selected people, while major areas of practice remain controversial. Consensus guidance is useful because it explains the reasoning and technical variables, but consensus is not the same as certainty for an individual patient.
References
- Consensus practice guidelines on interventions for lumbar facet joint pain from a multispecialty, international working group. Regional Anesthesia and Pain Medicine, 2020-04-03.
- Best practice in radiofrequency denervation of the lumbar facet joints: a consensus technique. British Journal of Pain, 2020.