
The anatomical target defines the procedure.
Facet procedures
Facet Joint Injection
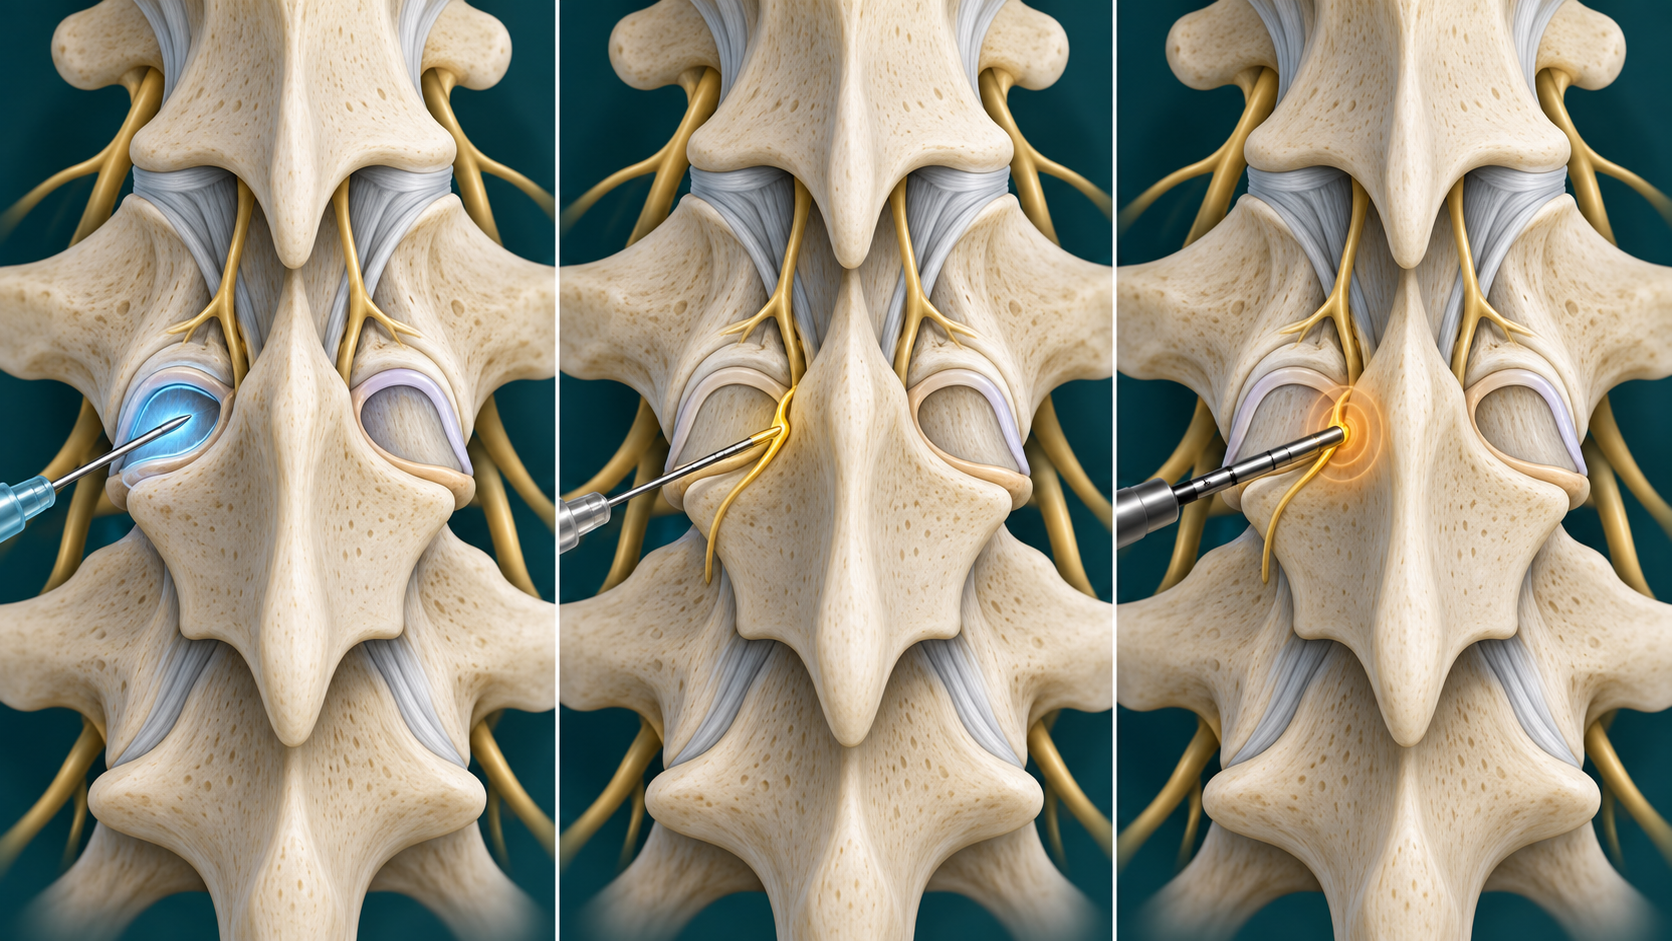
A facet joint injection places medication inside a spinal facet joint. That target differs from a medial branch block or radiofrequency ablation, both of which act near nerves outside the joint.
Quick orientation
What to know first
Selection depends on diagnosis, prior care, risks, and a question the procedure can answer.
No block or injection automatically commits a patient to another procedure.
Target and mechanism
The target defines the procedure
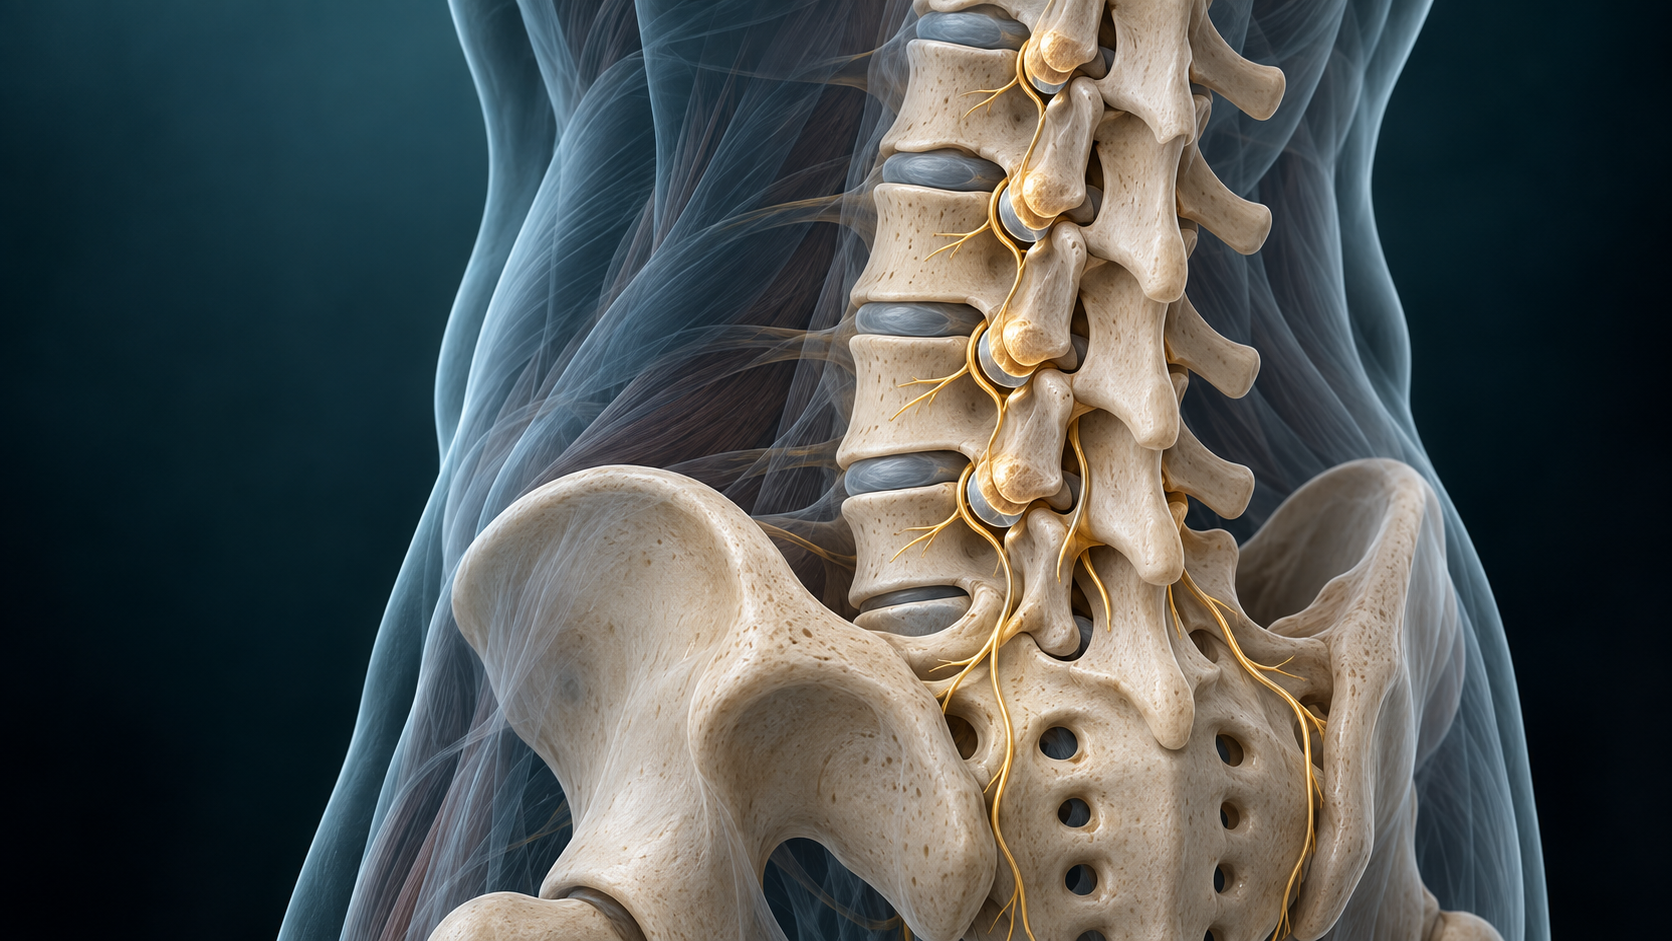
The needle enters the facet joint space under image guidance. Joint access can be technically limited by anatomy or degeneration, and an intra-articular response does not establish that every symptom comes from the joint.
Patient selection
Selection questions
Selection begins with a specific clinical question and an anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether the result would change care. No related listing, scan finding, or isolated examination maneuver establishes candidacy.
A predominantly axial pain pattern that plausibly matches the proposed target
Appropriate evaluation and conservative care have not resolved the decision
The result is expected to change the treatment plan
No medical or anatomic factor makes the procedure unsuitable
A staged decision
How we decide what may come next
The clinician first identifies the question the injection is intended to answer. Under image guidance, a fine needle enters the selected joint and a limited volume is injected according to the individualized plan. The response and adverse effects are reassessed; no automatic next procedure follows.
Related care
Conditions this treatment may be considered for
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Alternative
Cervical Facet Joint Pain
Alternative facet intervention only when anatomy, diagnostic purpose, and treatment plan support it.
Explore this pageAlternative
Lumbar Facet Joint Pain
Alternative facet intervention only when anatomy, diagnostic purpose, and treatment plan support it.
Explore this pageAlternative
Facet Joint Pain
Alternative facet intervention context without replacing regional diagnosis and treatment pages.
Explore this pageDecision process
Decision sequence
A diagnostic procedure provides information rather than an obligation to proceed. The response must be compared with the expected medication window, the usual pain, and meaningful activities. An unclear or discordant result should reopen the diagnosis and alternatives instead of triggering an automatic next procedure.
Review the pain pattern, neurologic symptoms, imaging, and prior care
Set measurable pain and functional goals before any procedure
Choose the next step from the full clinical picture rather than one isolated test
Evidence at a glance
Evidence at a glance
Study results depend on selection, comparator, technique, outcome, and follow-up.
Evidence for durable therapeutic benefit from intra-articular facet injections is sparse, heterogeneous, and generally low certainty.
Consensus guidelines do not recommend routine therapeutic facet injections or routine corticosteroid use in many settings.
Selected exceptions may exist, but those decisions require clinical review and should not be presented as a standard sequence.
Decision quality matters
Evidence, limits, and who it may fit
A listed option or diagnostic response does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Evidence, risks, and limits
Evidence for durable therapeutic benefit from intra-articular facet injections is sparse, heterogeneous, and generally low certainty. Consensus guidelines do not recommend routine therapeutic facet injections or routine corticosteroid use in many settings. Selected exceptions may exist, but those decisions require clinical review and should not be presented as a standard sequence.
Symptoms, examination, and imaging do not identify a painful facet joint with certainty.
A diagnostic response can be false-positive or false-negative.
Procedure choice, number of blocks, response threshold, medication, and technique require individualized clinical judgment.
The visit
What to expect from an evaluation
The visit should define the diagnosis, intended target, evidence, alternatives, risks, and the next useful decision. It should also separate clinical recommendations from insurance requirements, address medication and health factors, and explain what would count as an interpretable result without presenting one threshold as universal.
Common questions
Facet Joint Injection FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
How is this different from a medial branch block?
A facet injection enters the joint. A medial branch block places anesthetic near the nerve that carries sensation from the joint.
Is steroid always used?
No. Medication choice is individualized, and recent guidance advises against routine corticosteroid use in many facet procedures.
Does an injection automatically lead to RFA?
No. These are distinct procedures with different targets and roles.
Question before procedure
Start with a target-specific consultation
A consultation can clarify whether this procedure, another treatment, or continued diagnostic work fits the clinical picture.
