
Facet-related pain is a clinical hypothesis, not an imaging diagnosis.
Facet-mediated pain
Cervical Facet Joint Pain
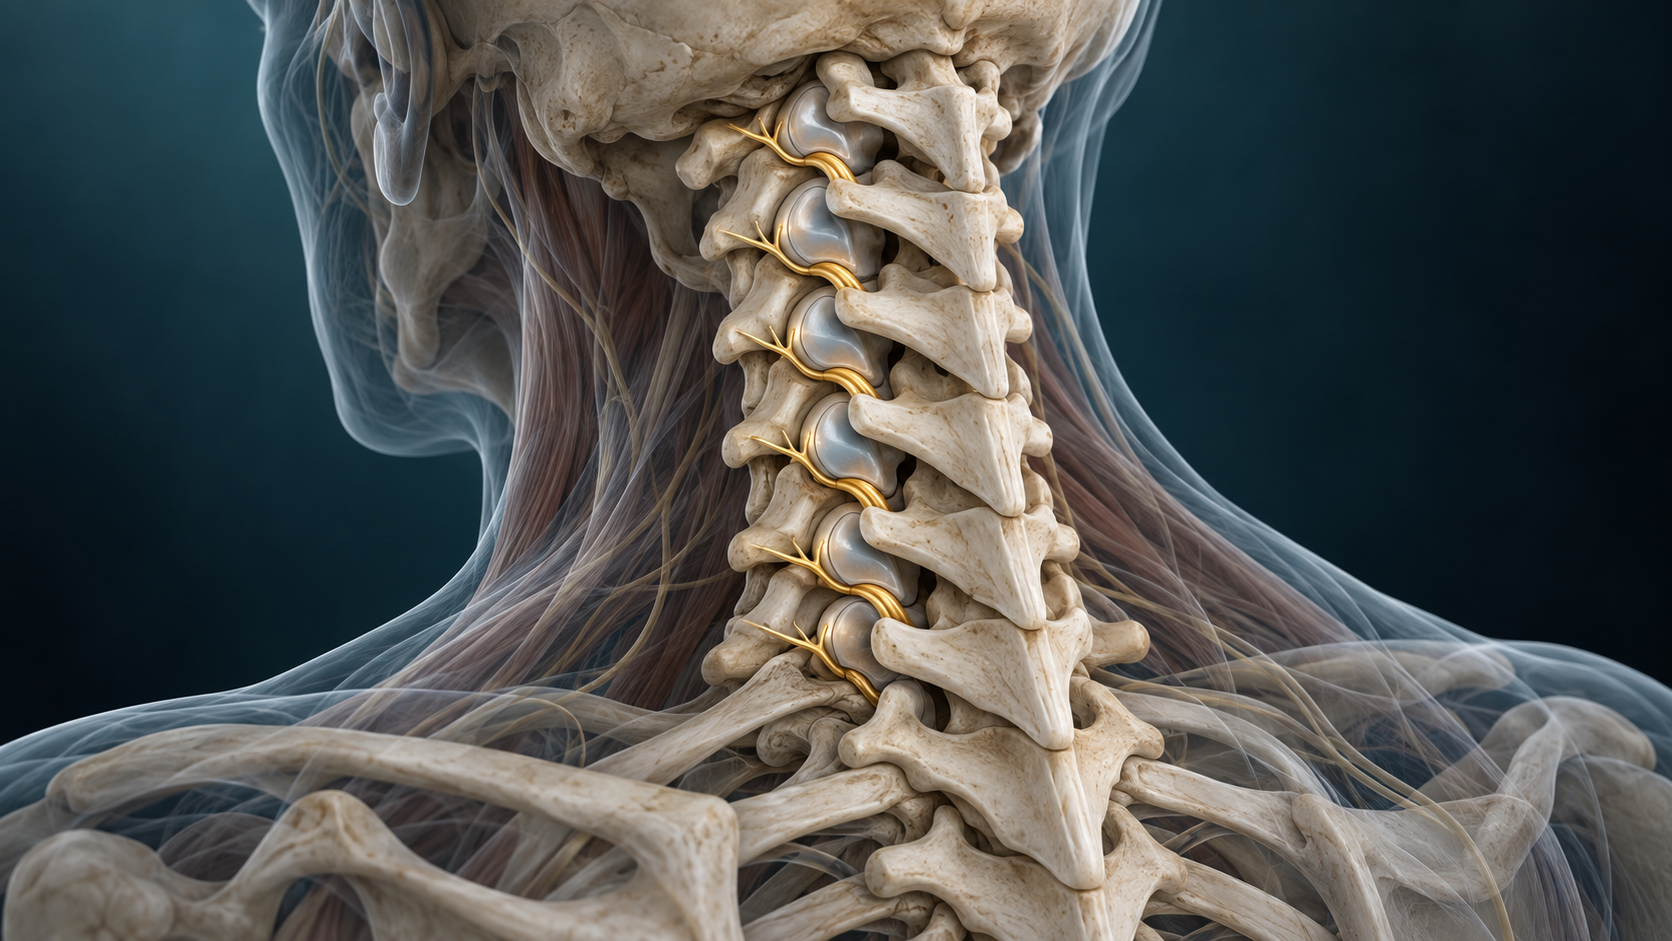
Cervical facet-mediated pain is one possible source of axial neck pain and referred pain toward the shoulder or head. No single symptom, examination maneuver, or scan confirms the diagnosis.
Quick orientation
What to know first
History and examination help locate the problem but are not definitive.
A diagnostic block may inform a later decision; it does not obligate treatment.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
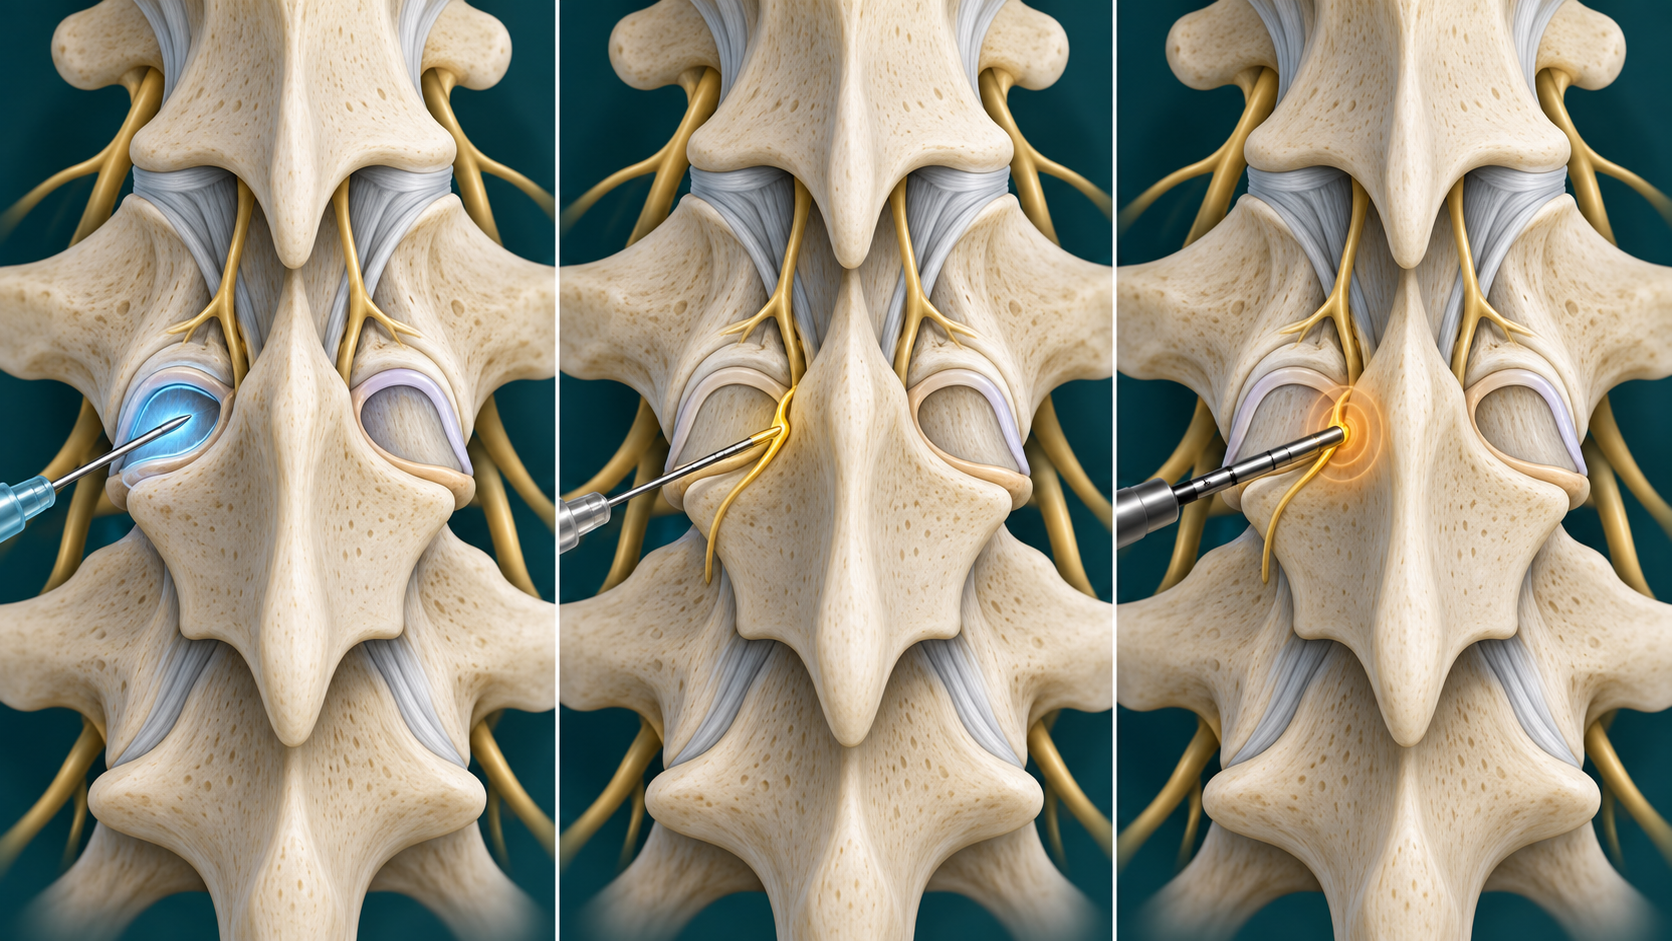
Cervical Medial Branch Block
Primary diagnostic/prognostic pathway for suspected cervical facet-mediated pain.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Cervical Radiofrequency Ablation
Later therapeutic step after appropriate diagnostic block response and review.
Alternatives, not a sequence
These options may be considered separately; one does not automatically lead to another.
Selected alternative
Facet Joint Injection
Alternative facet intervention only when anatomy, diagnostic purpose, and treatment plan support it.
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Symptom guide
Neck Pain
Broad neck-pain orientation across mechanical, degenerative, facet, stenotic, and radicular causes.
Open this guideClinical guide
Cervical Spondylosis
Degenerative cervical-spine changes when they are clinically relevant to symptoms, evaluation, and care.
Open this guideClinical guide
Cervical Spinal Stenosis
Cervical canal narrowing, possible cord or nerve effects, gait/hand warning features, and referral-aware evaluation.
Open this guideClinical guide
Cervical Radiculopathy
Cervical nerve-root symptoms into the shoulder, arm, or hand and their evaluation and treatment pathways.
Open this guideCare overview
Facet Joint Pain
Comparison and orientation for facet-mediated pain across cervical and lumbar regions.
Open this guideClinical guide
Lumbar Facet Joint Pain
Region-specific lumbar facet-mediated pain, diagnostic medial branch block considerations, and possible RFA pathway.
Open this guideSymptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms can help define a pattern, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation. A familiar pattern can still have more than one contributor, and a change in pattern may require a different assessment.
Pain is often axial rather than dominated by limb symptoms.
Movement, posture, or sustained loading may change symptoms.
The pattern overlaps with disc, muscle, sacroiliac, nerve-root, and other pain sources.
Relevant anatomy
Anatomy and pain mechanisms
Cervical facet joints pair adjacent vertebrae and receive sensory input from small medial branch nerves. Upper cervical structures can refer pain toward the head, while lower levels more often refer toward the neck and shoulder; overlap is common.
History and examination first
How the diagnosis is evaluated
Evaluation starts with history, examination, neurologic screening, and review of prior care. Imaging may identify degeneration or exclude another concern, but common facet changes can also appear in people without pain. A carefully performed diagnostic block may be considered when the result would change management.
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Disc-related pain
Myofascial pain
Sacroiliac pain
Radiculopathy or spinal stenosis
Fracture, infection, inflammatory disease, or another urgent cause when clinical features suggest it
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects function.
Education and paced activity
Exercise or physical therapy matched to the diagnosis
Medication review and risk reduction
Reassessment when the pattern changes or does not respond as expected
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Imaging findings correlate poorly with a painful facet source.
Consensus recommendations differ on selection thresholds and block protocols.
Recent placebo-controlled syntheses report small or uncertain average benefits, while selected-patient reviews report more favorable RFA outcomes.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
New or progressive weakness
Bowel or bladder dysfunction or saddle numbness
Fever, unexplained weight loss, major trauma, cancer history, or rapidly worsening pain
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty, distinguish clinical evidence from coverage rules, and define what information a test or treatment is expected to add before it is performed.
Review the pain pattern, neurologic symptoms, imaging, and prior care
Set measurable pain and functional goals before any procedure
Choose the next step from the full clinical picture rather than one isolated test
Common questions
Cervical Facet Joint Pain FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Can cervical facet pain cause headache?
Upper cervical structures can refer pain toward the head, but cervicogenic headache requires a separate diagnosis and other headache causes must remain open.
Can MRI identify the painful joint?
No. Imaging can support evaluation or reveal alternatives, but common changes do not identify a painful joint with certainty.
Is a medial branch block treatment?
Its main role in this pathway is diagnostic or prognostic, and the response requires careful interpretation.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
