
The symptom region is a starting point, not a diagnosis.
Neck conditions
Cervical Spondylosis
Cervical spondylosis describes age- and load-related degenerative changes in the neck. These imaging findings are common and become clinically relevant only when they fit the symptoms, examination, and functional problem.
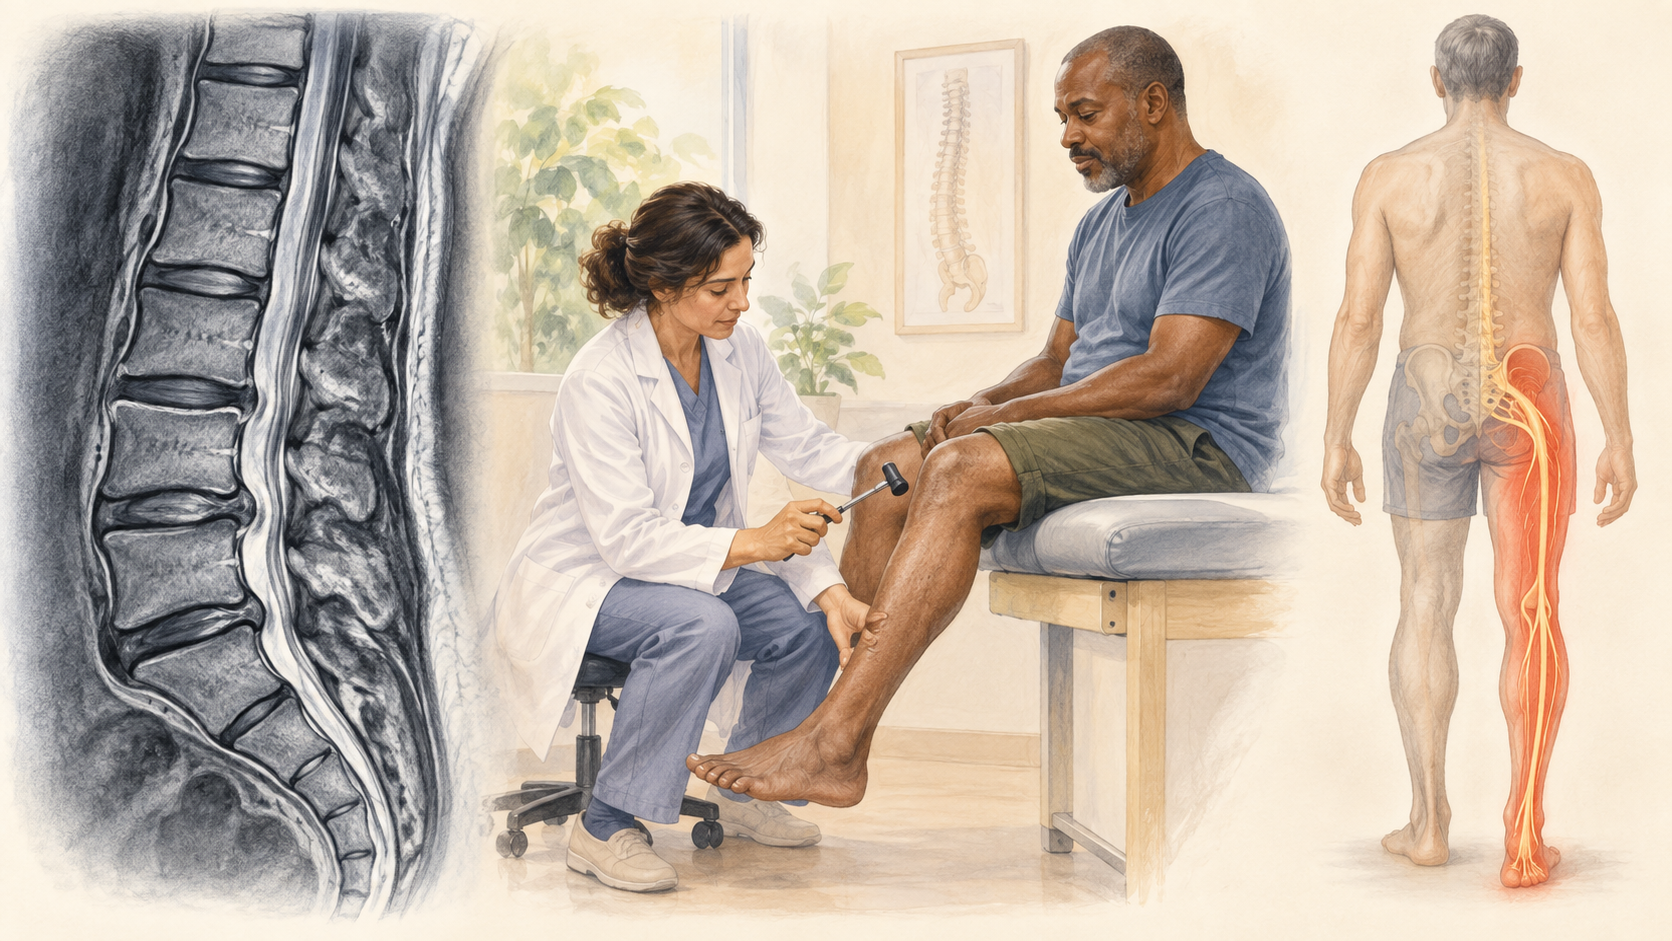
Quick orientation
What to know first
History and examination determine which anatomy and tests matter.
Urgent, neurologic, infectious, vascular, traumatic, and systemic causes stay visible until reasonably excluded.
What we may consider next
How we may treat this
These options depend on the diagnosis, exam findings, prior care, goals, and individual risk review. A listed pathway does not establish candidacy or guarantee a later procedure.
Establish first
Diagnostic or prognostic steps help clarify the pain generator or whether a later option fits.
Diagnostic / prognostic step
Cervical Medial Branch Block
Diagnostic/prognostic step when clinical evaluation suggests a cervical facet-mediated pain generator; imaging findings alone do not establish the pain generator or procedural candidacy.
May come later
A later procedure is considered only when evaluation and the response to earlier steps support it.
Later treatment option
Cervical Radiofrequency Ablation
Later treatment option for selected facet-mediated axial neck pain only after appropriate evaluation and a supportive diagnostic/prognostic block response; progression is not automatic.
Choose the guide that matches your question
Explore the specific guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Symptom guide
Neck Pain
Broad neck-pain orientation across mechanical, degenerative, facet, stenotic, and radicular causes.
Open this guideClinical guide
Cervical Facet Joint Pain
Region-specific cervical facet-mediated pain, diagnostic medial branch block considerations, and possible RFA pathway.
Open this guideClinical guide
Cervical Spinal Stenosis
Cervical canal narrowing, possible cord or nerve effects, gait/hand warning features, and referral-aware evaluation.
Open this guideClinical guide
Cervical Radiculopathy
Cervical nerve-root symptoms into the shoulder, arm, or hand and their evaluation and treatment pathways.
Open this guideSymptoms are clues, not a diagnosis
What the pattern can feel like
Symptoms help define a syndrome, but they do not confirm which structure is responsible. Distribution, timing, aggravating factors, neurologic findings, function, and important alternatives all shape the evaluation.
Location, radiation, timing, quality, sensory change, weakness, stiffness, swelling, activity, position, sleep, and function help define the pattern.
Similar symptoms may arise from a joint, tendon, muscle, spine, peripheral nerve, circulation, or systemic condition.
Imaging and test abnormalities require clinical correlation and may not identify the symptom source.
Relevant anatomy
Anatomy and pain mechanisms
Discs, endplates, facet joints, ligaments, nerve-root openings, and the spinal canal may change over time. A degenerative label does not by itself identify a painful structure, radiculopathy, or spinal cord problem.
History and examination first
How the diagnosis is evaluated
Evaluation begins with the patient question, safety screen, history, and focused examination. Testing is selected only when it can clarify a competing diagnosis, guide treatment, or change referral urgency.
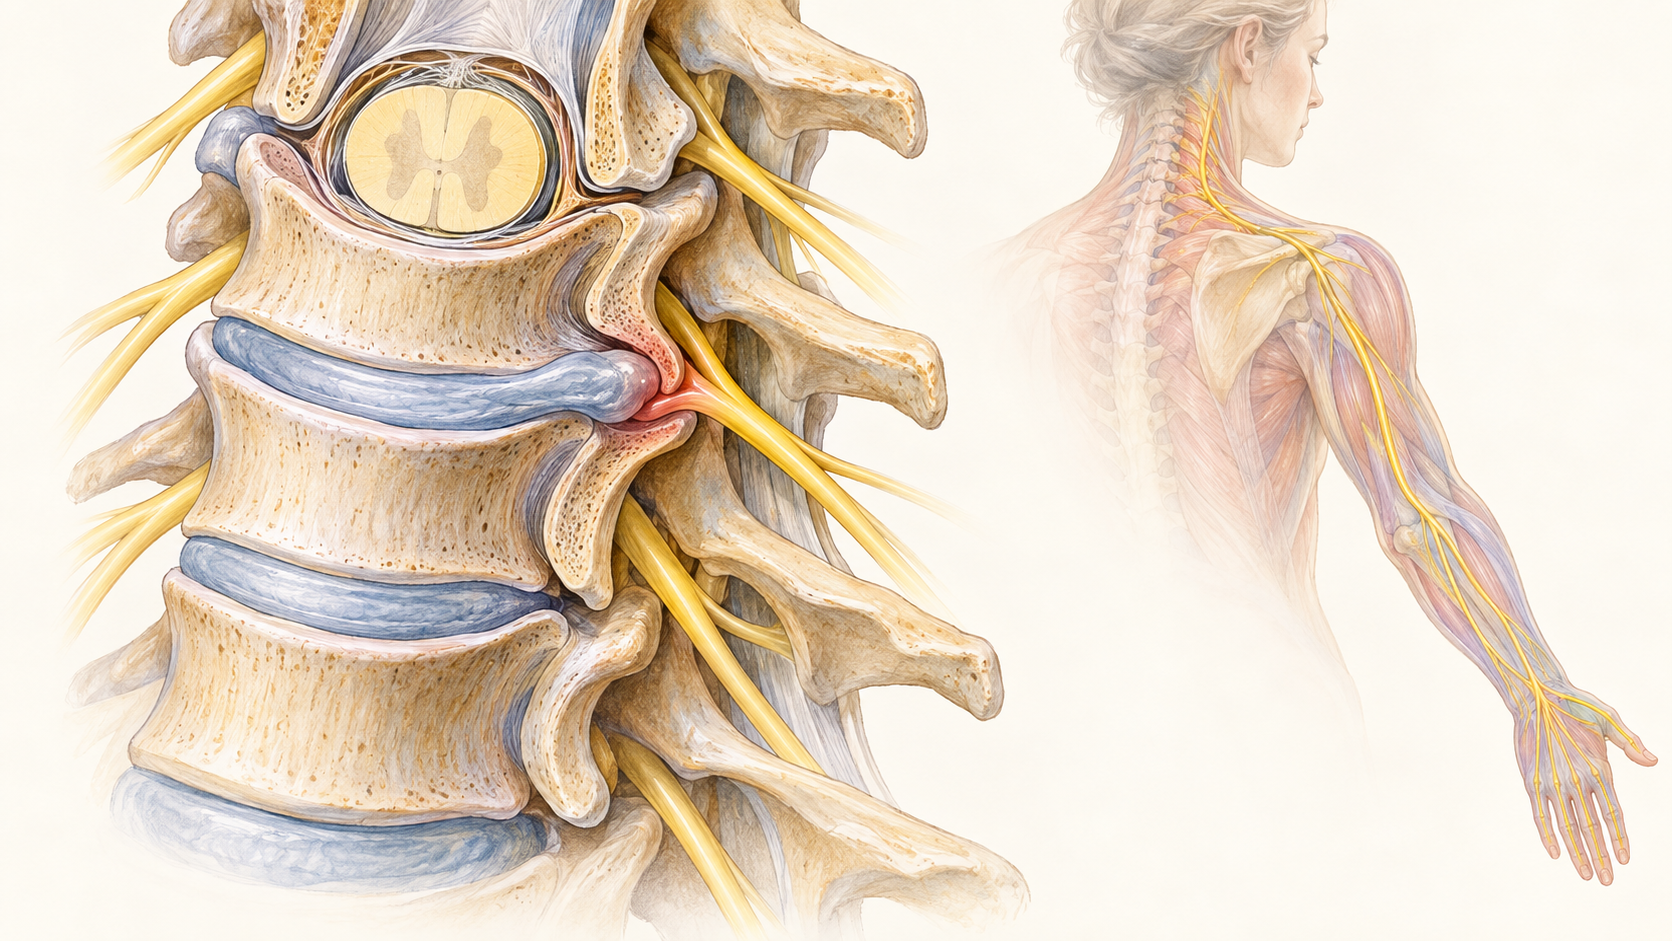
Keep the differential open
What else can look similar
Keep common and serious alternatives open until the evidence supports a narrower conclusion.
Local joint, tendon, muscle, ligament, bursa, bone, or soft-tissue disorders
Spinal referral, nerve-root, plexus, or peripheral-nerve disorders
Traumatic, infectious, inflammatory, vascular, metabolic, medication-related, or oncologic causes
Core care
Conservative and coordinated care
Procedure discussions belong inside a broader plan that protects neurologic function and daily activity.
Education, pacing, sleep and activity strategies matched to the diagnosis
Rehabilitation focused on mobility, strength, tolerance, and function when safe
Medication and comorbidity review with the appropriate clinician
Reassessment when symptoms, neurologic findings, function, or response changes
Evidence at a glance
Evidence at a glance
Evidence strength, comparator, follow-up, and selection affect interpretation.
Degenerative cervical findings are interpreted with symptoms and examination rather than treated as a stand-alone pain diagnosis.
Imaging choice depends on red flags, neurologic features, duration, and the question being asked.
Facet, nerve-root, and canal-narrowing syndromes retain separate diagnostic ownership.
Decision quality matters
Evidence, limits, and who it may fit
A listed option does not establish candidacy. Diagnosis, anatomy, prior care, risk, alternatives, goals, and evidence must align.
Referral and urgent signs
When urgent or different evaluation matters
These findings can change the timing or destination of care.
New or worsening arm or hand weakness, loss of hand coordination, balance change, gait difficulty, or widespread numbness that may suggest spinal cord involvement
New bowel or bladder dysfunction together with limb weakness, gait change, or other signs of spinal cord dysfunction
Fever, major trauma, cancer history, unexplained weight loss, severe night pain, or another concern for infection, fracture, inflammatory disease, or cancer
The visit
What to expect at an evaluation
The visit should narrow the diagnosis, identify safety and referral needs, review imaging and prior care in context, and choose the next useful decision. The clinician should explain uncertainty and what a treatment is expected to add before it is performed.
Define the location, timing, triggers, sensory features, functional effect, prior injury, and prior care
Examine the relevant joint, spine, muscles, nerves, circulation, gait, strength, sensation, and reflexes as appropriate
Use imaging, electrodiagnostic testing, laboratory work, or referral only when it answers a clinical question
Choose education, rehabilitation, medical care, further diagnostic work, a selected procedure discussion, or referral based on the working diagnosis
Common questions
Cervical Spondylosis FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
For Cervical Spondylosis, does the location alone establish the diagnosis?
No. Several tissues and referred pathways can produce pain in the same region.
Do I always need imaging for Cervical Spondylosis?
No. Testing is chosen when it can answer a clinical question or change care.
Why is a treatment guide listed with Cervical Spondylosis?
Related guides are educational and do not establish a diagnosis or treatment recommendation.
Diagnosis before procedure
Start with a careful evaluation
A focused evaluation can clarify the diagnosis, important alternatives, and the next step that fits the clinical picture.
