
The target is selected from a concordant radicular pattern, not from imaging alone.
Epidural steroid injections
Lumbar Epidural Steroid Injection
A lumbar epidural steroid injection may be discussed for selected nerve-root symptoms into the leg when the diagnosis and target are coherent. It does not treat every form of low-back pain and does not repair a disc or reverse stenosis.
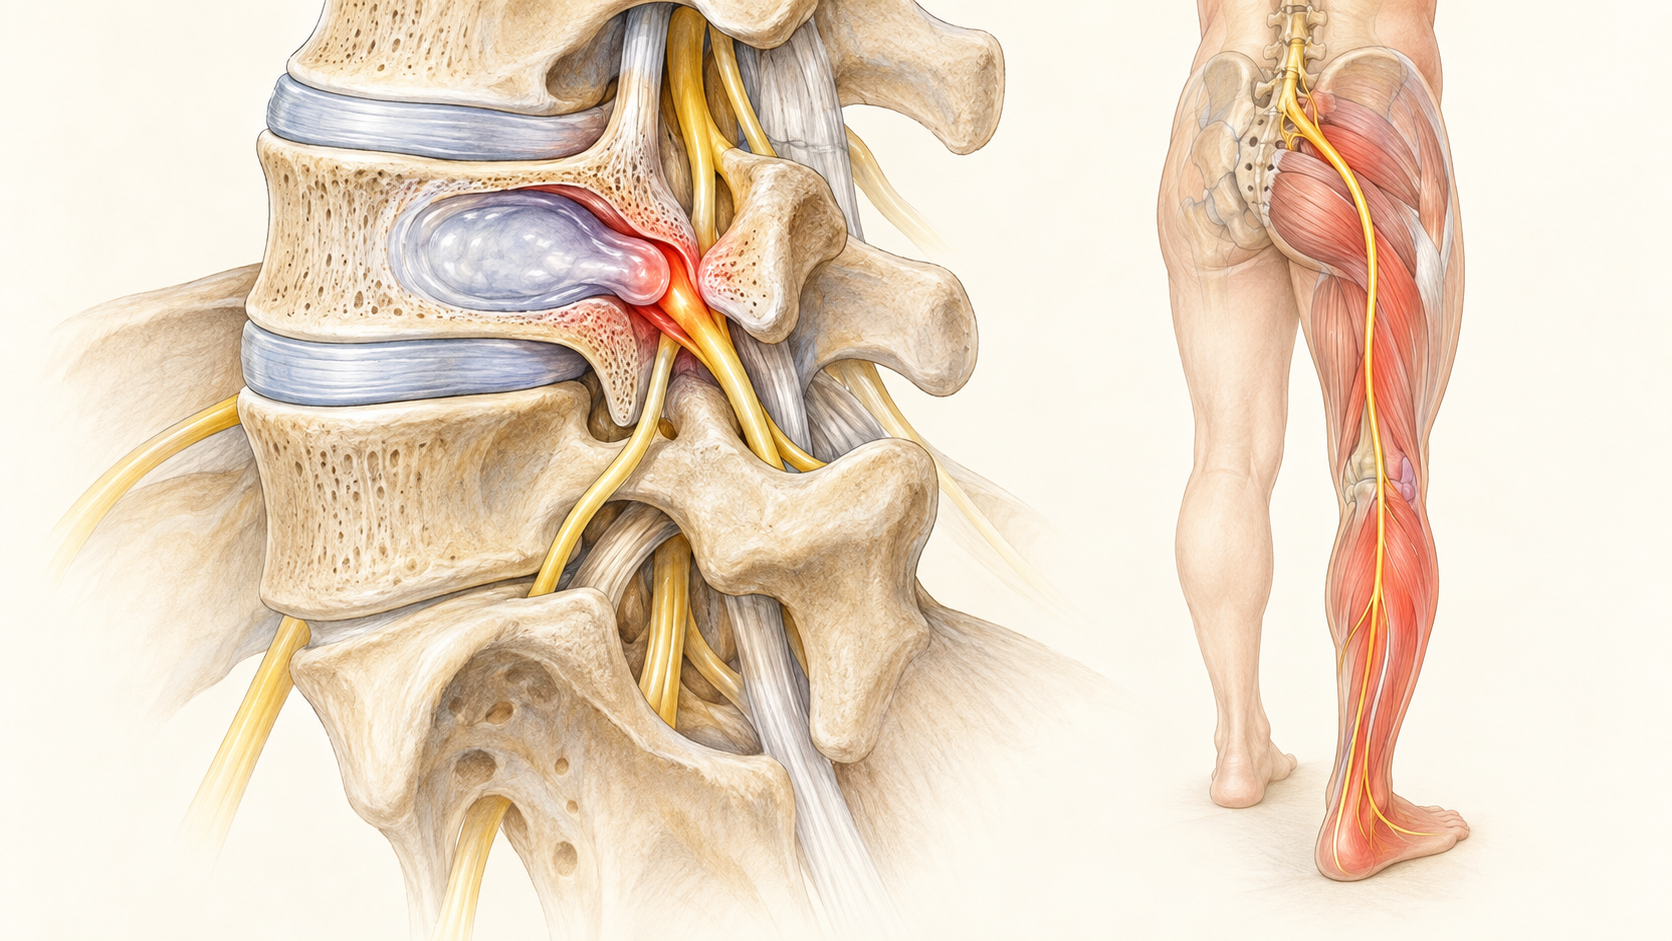
Quick orientation
What to know first
Any average benefit is generally modest and more evident in the short term.
Epidural corticosteroid use is off-label and rare serious neurologic harms have been reported.
Learn what may come next
Related guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Related treatments
Epidural Steroid Injections
Compare the ESI family, general sequence, limitations, and cervical, lumbar, and caudal variants.
Open this guideSpecific treatment
Cervical Epidural Steroid Injection
Cervical ESI anatomy, selection context, procedure considerations, risks, and recovery.
Open this guideSpecific treatment
Caudal Epidural Steroid Injection
Caudal epidural access, selection context, procedure considerations, risks, and recovery.
Open this guideTarget and mechanism
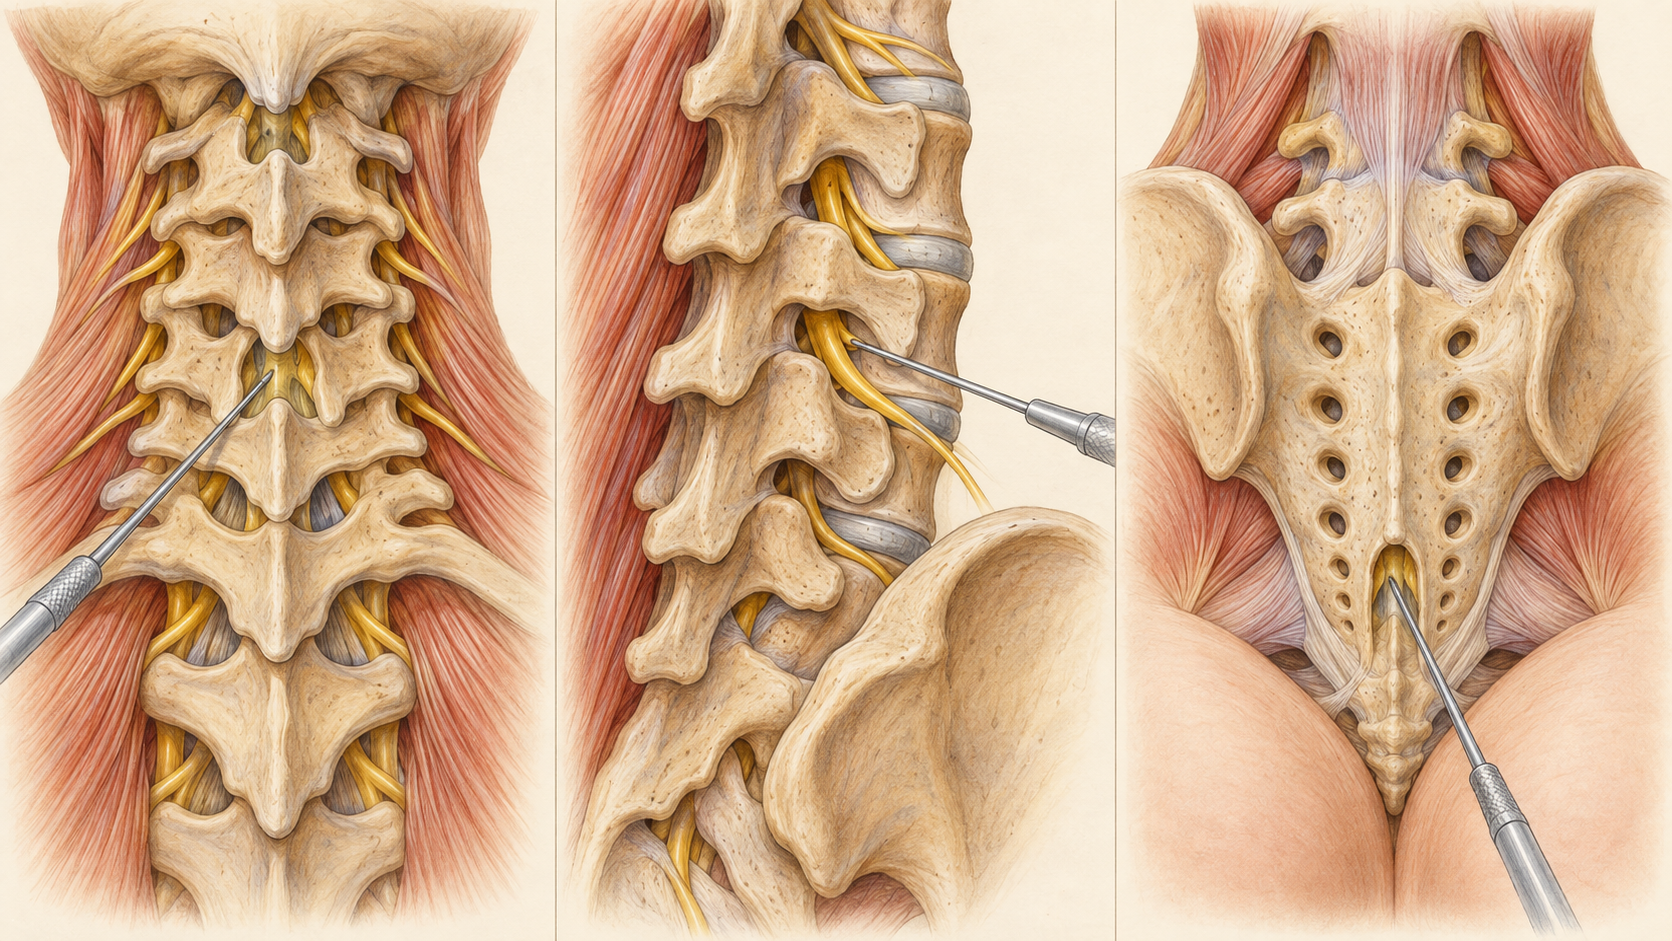
The target defines the procedure
Lumbar epidural access can be planned through different image-guided routes according to the affected root, level, anatomy, prior surgery, and risk profile. The access route is a technical decision, not a guarantee of broader or longer relief.
Patient selection
Selection questions
Selection begins with a clinically coherent radicular syndrome and a specific anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether a procedure is the right next decision.
A clinically coherent radicular symptom pattern
Imaging or other findings that support the intended anatomic target when imaging is indicated
Persistent functional limitation despite appropriate initial care or a time-sensitive reason for a procedure discussion
A risk review that supports proceeding and a clear plan for reassessment
A staged decision
How we decide what may come next
The clinician confirms the radicular pattern and intended target, reviews alternatives and medical risks, and selects a route and medication plan. Pain and meaningful function are reassessed afterward. A limited or absent response should reopen the diagnosis and options rather than trigger an automatic series.
Related care
Conditions this treatment may be considered for
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Needs a separate clinical evaluation
Lumbar Radiculopathy / Sciatica
May be considered for selected lumbar nerve-root symptoms when findings correlate.
Explore this pageNeeds a separate clinical evaluation
Lumbar Spinal Stenosis
May be considered for selected radicular symptoms; it does not treat every stenosis presentation.
Explore this pageNeeds a separate clinical evaluation
Herniated Disc
Region-specific option only when lumbar disc pathology and nerve-root symptoms correlate; imaging alone is insufficient.
Explore this pageDecision process
Decision sequence
An epidural injection is an optional treatment discussion, not an automatic step. The response must be reassessed against the usual symptoms and meaningful activities. A limited, absent, or discordant response should reopen the diagnosis and alternatives instead of triggering an automatic series.
Confirm the diagnosis and intended target
Review alternatives, medications, medical risks, and the off-label status of epidural corticosteroid use
Define measurable functional goals and a reassessment plan before proceeding
Evidence at a glance
Evidence at a glance
Study results depend on diagnosis, selection, comparator, technique, outcome, and follow-up.
For selected lumbar radicular pain, systematic reviews find a modest average short-term benefit with uncertainty about durable benefit.
An epidural injection does not repair a disc or reverse stenosis, and evidence for stenosis-associated pain is limited.
Lumbar route, diagnosis, comparator, follow-up, and selection vary across studies, so average results do not predict one person’s response.
Decision quality matters
Evidence, limits, and who it may fit
A related listing or scan finding does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Evidence, risks, and limits
For selected lumbar radicular pain, systematic reviews find a modest average short-term benefit with uncertainty about durable benefit. An epidural injection does not repair a disc or reverse stenosis, and evidence for stenosis-associated pain is limited. Lumbar route, diagnosis, comparator, follow-up, and selection vary across studies, so average results do not predict one person’s response.
An injection does not repair a disc, reverse stenosis, or guarantee that surgery can be avoided.
Bleeding, infection, allergic or medication effects, transient symptom change, and rare serious neurologic injury require individualized consent.
Route, medication, frequency, sedation, medication holds, and aftercare are clinician decisions and are not universal protocols.
The visit
What to expect from an evaluation
The visit should define the diagnosis, intended target, evidence, alternatives, off-label medication use, risks, and the next useful decision. Route, medication, frequency, sedation, medication holds, and aftercare remain individualized clinician decisions.
Common questions
Lumbar Epidural Steroid Injection FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is this for all low-back pain?
No. The clearest evidence relates to selected radicular leg pain, not nonspecific axial low-back pain.
Does it fix a herniated disc?
No. It may reduce inflammation around a selected nerve root but does not repair the disc.
Will I need a series of injections?
There is no universal series. Any repeat decision depends on the diagnosis, response, function, risks, and alternatives.
Question before procedure
Start with a diagnosis-first consultation
A consultation can clarify whether an epidural injection, another treatment, continued conservative care, or referral fits the clinical picture.
