
The diagnosis and anatomic target come before the procedure.
Joint and musculoskeletal treatments
Sacroiliac Joint Injection
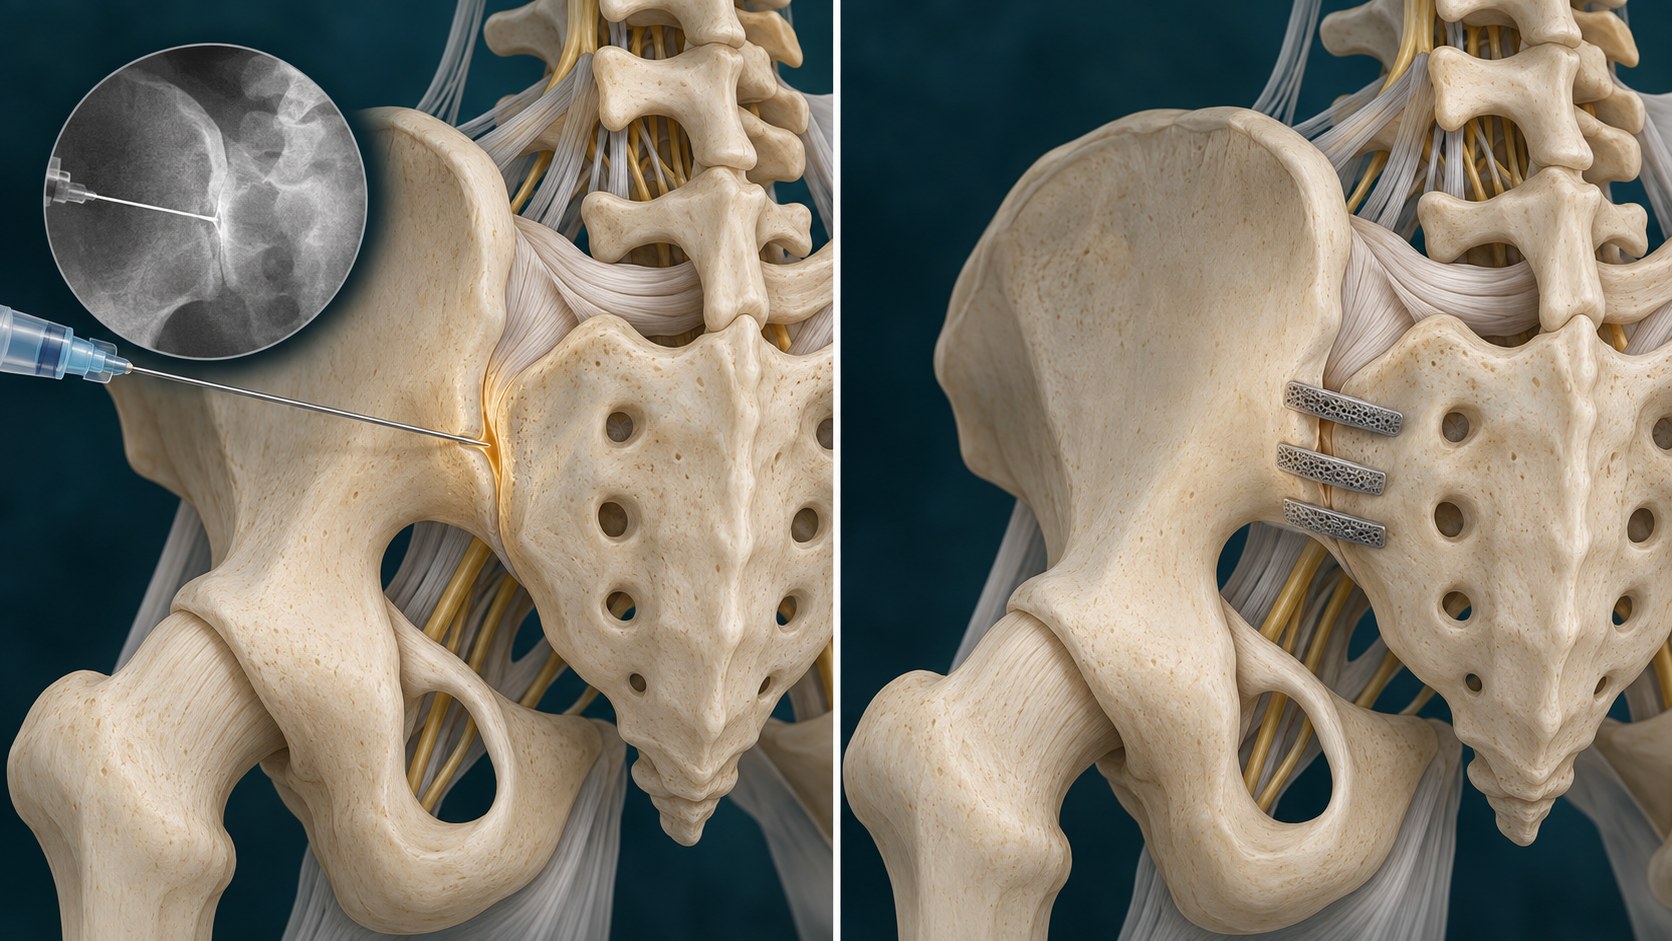
A sacroiliac joint injection places medication into the joint under image guidance. It may be used to add diagnostic information or for a selected therapeutic goal, but the result is interpreted with the complete clinical picture.
Quick orientation
What to know first
Medication, route, frequency, and aftercare are individualized rather than universal.
A response can inform the plan, but it does not automatically establish a diagnosis or require another procedure.
Learn what may come next
Related guides.
Use these links to learn about related symptoms, conditions, and treatments. An individual evaluation is still needed to determine a diagnosis or whether a treatment may be appropriate.
Care overview
Sacroiliac Joint Treatments
Compare sacroiliac diagnostic and treatment pathways.
Open this guideClinical guide
Sacroiliac Joint Pain
Sacroiliac-joint pain patterns, evaluation, differential diagnosis, and treatment pathways.
Open this guideSpecific treatment
Posterior Sacroiliac Joint Fusion
Understand posterior SI-joint fusion selection, limitations, risks, and recovery.
Open this guideTarget and mechanism
The target defines the procedure
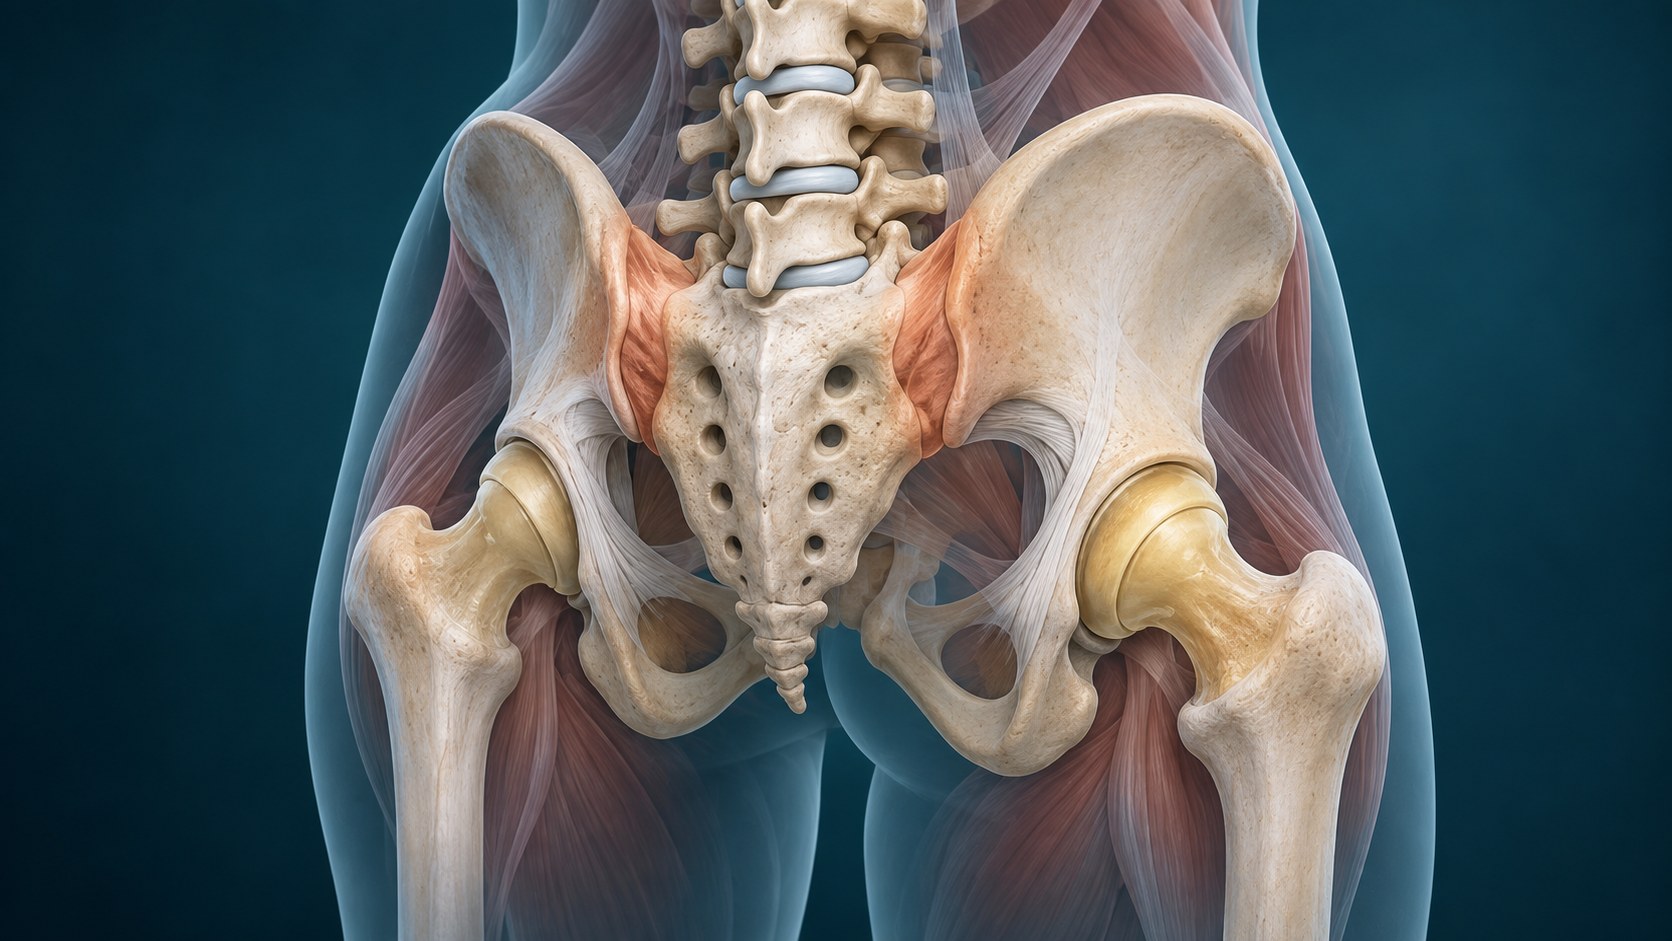
The SI joint is narrow, irregular, and surrounded by pain-sensitive ligaments. An intra-articular injection targets the joint space; it does not test every extra-articular structure in the SI joint complex.
Patient selection
Selection questions
Selection begins with a clinically coherent diagnosis and a specific anatomic target. It also considers competing diagnoses, prior treatment, medication and bleeding risk, infection risk, goals, and whether a procedure is the right next decision.
A clinically coherent diagnosis and target
Persistent meaningful functional limitation despite appropriate initial care or a clear diagnostic question
A risk review that supports proceeding
A defined goal and reassessment plan
A staged decision
How we decide what may come next
The clinician confirms the intended joint and clinical question, reviews alternatives and risks, and uses image guidance and contrast when appropriate to verify position. The usual symptoms and function are reassessed afterward. A positive, limited, or absent response each has uncertainty.
Related care
Conditions this treatment may be considered for
These related guides show educational connections. They do not establish candidacy, a recommendation, or a required sequence.
Needs a separate clinical evaluation
Sacroiliac Joint Pain
May contribute to a diagnosis-specific injection pathway and selected therapeutic assessment.
Explore this pageDecision process
Decision sequence
A procedure is an optional treatment discussion, not an automatic step. The response must be reassessed against the usual symptoms and meaningful activities. A limited, absent, or discordant response should reopen the diagnosis and alternatives instead of triggering an automatic series.
Confirm the diagnosis and intended target
Review alternatives and medical risks
Define meaningful pain and functional goals
Reassess the result before deciding what comes next
Evidence at a glance
Evidence at a glance
Study results depend on diagnosis, selection, comparator, technique, outcome, and follow-up.
Diagnostic injections are imperfect reference tests and can have false-positive and false-negative results.
Therapeutic injection evidence is mixed and limited by variable diagnosis, technique, comparator, and follow-up.
An injection response does not automatically create a fusion pathway.
Decision quality matters
Evidence, limits, and who it may fit
A listed option or imaging finding does not establish candidacy. Evidence and uncertainty must be matched to the individual question.
Risks and limits
Evidence, risks, and limits
Diagnostic injections are imperfect reference tests and can have false-positive and false-negative results. Therapeutic injection evidence is mixed and limited by variable diagnosis, technique, comparator, and follow-up. An injection response does not automatically create a fusion pathway.
Bleeding, infection, allergic or medication effects, transient symptom change, and target-specific injury require individualized consent.
Medication selection, volume, frequency, sedation, medication holds, driving, and follow-up are not universal protocols.
A procedure does not replace rehabilitation, urgent evaluation, or surgical consultation when those are more appropriate.
The visit
What to expect from a consultation
The visit should define the diagnosis, intended target, evidence, alternatives, risks, and the next useful decision. Medication, frequency, sedation, medication holds, driving, and aftercare remain individualized clinician decisions.
Common questions
Sacroiliac Joint Injection FAQ
These answers are educational and cannot determine an individual diagnosis or treatment plan.
Is the injection diagnostic or therapeutic?
It can be used for either purpose, but the clinical question, medication, and interpretation should be defined beforehand.
Does relief prove the SI joint is the only pain source?
No. Technical and biologic factors can affect the response, and more than one pain source may coexist.
Does a helpful injection mean fusion is required?
No. It is one data point in a broader selection process.
Question before procedure
Start with a diagnosis-first consultation
A consultation can clarify whether a selected procedure, another treatment, continued conservative care, or referral fits the clinical picture.
